What the Anion Gap Represents
The anion gap is a calculated value from routine electrolytes that helps clinicians assess acid-base balance. It is commonly derived from serum sodium, serum chloride, and serum bicarbonate, and it provides a practical clue to hidden acids in the blood. In simple terms, the anion gap calculation compares measured positively charged and negatively charged ions in serum chemistry to estimate whether unmeasured anions are accumulating.
This is where an anion gap calculator becomes useful. By rapidly organizing the laboratory values, it can help with faster recognition of a metabolic derangement. The result does not diagnose a condition by itself, but it can act as a diagnostic marker that points toward an acidotic state and helps refine the differential diagnosis.
The anion gap is especially important because many serious illnesses alter acid-base balance before the full clinical picture is obvious. In critical care, a changing anion gap may reflect worsening perfusion, evolving organ dysfunction, or a response to resuscitation. The number should always be interpreted in clinical context, not as an isolated lab result.
Why the Anion Gap Matters in Shock
Shock is a state of insufficient perfusion and reduced oxygen delivery to tissues. When tissues do not get enough oxygen, they turn toward anaerobic metabolism, which promotes lactate accumulation and can lead to lactic acidosis. This process often results in metabolic acidosis with an elevated anion gap.
The connection between shock and the anion gap is clinically significant because shock is not one single disease. Hypovolemic shock, cardiogenic shock, obstructive shock, and distributive shock can all lead to hemodynamic instability, but through varying mechanisms. Despite those differences, they may each cause tissue hypoperfusion and increasing lactate if oxygen delivery is inadequate.
In sepsis, the problem may include both impaired perfusion and abnormal cellular metabolism. In ischemia, tissues are directly deprived of blood flow. In either setting, the anion gap can provide a bedside clue that the body is under metabolic stress. A higher gap often implies that the acid-base problem is more than just dehydration or isolated electrolyte loss.
That said, the anion gap is not a perfect severity score. It is part of the broader picture that includes blood pressure, mental status, urine output, lactate, and response to resuscitation. Used well, it helps identify the biochemical footprint of shock and directs ongoing reassessment.
How to Determine the Anion Gap
Clinicians commonly calculate the anion gap from serum sodium, serum chloride, and serum bicarbonate. An anion gap calculator can streamline the math and limit transcription errors during time-sensitive decision-making. The usual formula is:
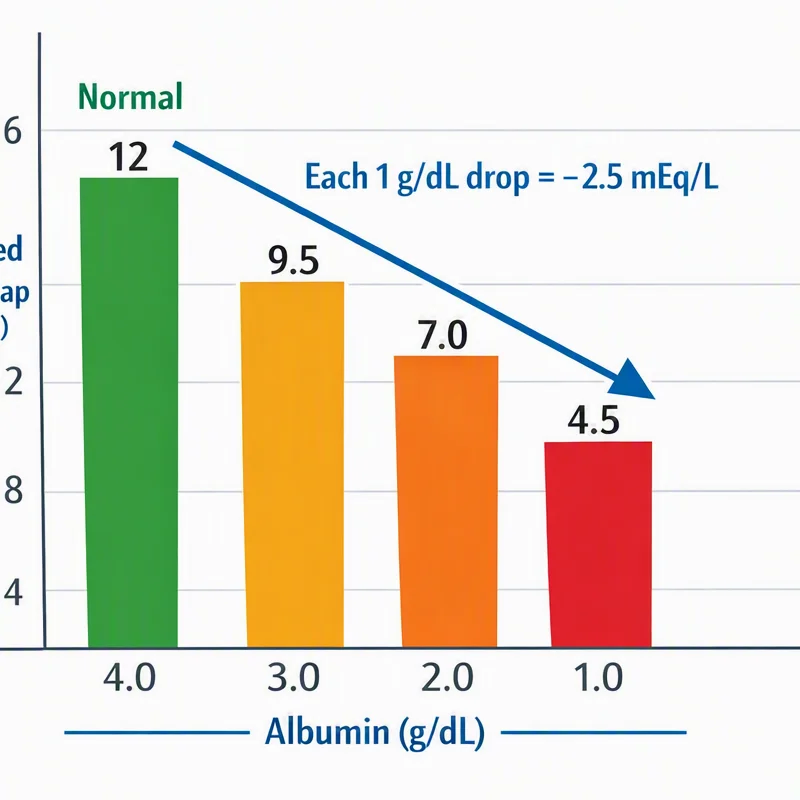
anion gap = sodium − (chloride + bicarbonate)Because albumin is a key unmeasured anion, low albumin can make the gap appear falsely normal or only mildly elevated. That is why albumin correction is important. A low measured gap may hide a true acid burden unless the corrected anion gap is calculated.
For many clinicians, the corrected value is more informative than the raw number in critically ill patients. If albumin is low, the correction can show a more accurate picture of acid-base status and support prompt recognition of high anion gap metabolic acidosis. This is especially useful in patients with serious illness, fluid shifts, inflammation, or prolonged hospitalization.
The anion gap should also be interpreted in conjunction with serum bicarbonate. A low bicarbonate level supports metabolic acidosis, but the gap determines whether the acidosis is likely due to unmeasured acids such as lactate, ketones, or toxins. In other words, the calculator is not just a number generator; it is a way to connect serum chemistry to the underlying cause of illness.
Sources of a High Anion Gap in Circulatory collapse
A increased anion gap in shock usually means hidden acids are building up. The most common cause is lactate. When perfusion is inadequate, cells generate energy through oxygen-independent pathways, and lactate increases. This is the typical pattern in lactic acidosis, especially when shock is prolonged or marked.
Sepsis is a common setting for raised lactate and a high anion gap. In septic shock, inflammatory mediators, microcirculatory dysfunction, and mitochondrial abnormalities may contribute to lactate elevation even when blood pressure is being stabilized. The anion gap can help underscore that the patient is experiencing metabolic stress, not just hypotension.
Ischemia from bowel compromise, limb ischemia, or other low-flow states can also elevate the gap. In these cases, the source of acid generation may be regional tissue injury, but the systemic laboratory pattern can still signal a critical process. The combination of rising gap and declining symptoms should prompt urgent evaluation.
Toxic ingestions are another important consideration. Toxic alcohols such as methanol and ethylene glycol can cause high anion gap metabolic acidosis and may coexist with shock-like physiology or organ dysfunction. They should remain on the differential diagnosis, especially when the clinical story does not fully fit perfusion failure alone.
Other contributors may include renal dysfunction, ketoacidosis, or mixed acid-base disorders, but in a patient with shock the first concern is often whether rising lactate reflects inadequate resuscitation or ongoing tissue hypoperfusion. The pattern should always be paired with hemodynamic data and repeat laboratory values.
Typical Anion Gap Does Not Rule Out Shock
A normal anion gap does not rule out shock. At the start of illness, the acid-base picture may still seem deceptively mild. This is particularly true in early shock, when tissue hypoperfusion is developing but lactate has not yet risen dramatically or has not yet been measured at the right time.
Shock may also present with normal anion gap metabolic acidosis. For instance, chloride-rich fluid administration may cause hyperchloremia and a non-anion-gap acidosis. In that case, the patient can remain critically ill even though the anion gap is not elevated. The acid-base pattern may shift as treatment progresses, making trend analysis important.
A arterial blood gas can provide additional context by showing pH, bicarbonate estimate, and respiratory compensation. Still, a normal or near-normal pH on blood gas does not exclude a serious process when compensation is masking the underlying disorder. The anion gap and the arterial blood gas should be interpreted together rather than in isolation.
For this reason, a normal gap should not reassure clinicians when the bedside picture points to low perfusion, altered mental status, oliguria, or increasing vasopressor needs. Shock is fundamentally a problem of oxygen delivery and organ dysfunction, and the laboratory pattern may lag behind the physiology.
Interpreting the Result in Context
The anion gap is most valuable when you interpret it in the context of the full bedside picture: blood gas, vital signs, urine output, mental status, and overall clinical assessment. A single number cannot distinguish every cause of metabolic acidosis, but it can increase suspicion for a specific process when the clinical pattern fits.
Base deficit is another useful marker in this context. A more negative base deficit often suggests a greater metabolic acid load and can support concern for shock-related hypoperfusion. When combined with lactate, base deficit may help assess the severity of the metabolic abnormality and the patient’s response to resuscitation.
Albumin correction is especially important in critical illness because low albumin can mask a clinically meaningful gap. In a patient with low albumin and borderline results, the corrected anion gap may reclassify the acid-base disorder and reveal an occult high anion gap metabolic acidosis. This matters for both diagnosis and treatment planning.
It is also helpful to think in terms of pattern recognition. A rising gap with worsening lactate suggests ongoing anaerobic metabolism or a new source of acid. A stable gap with normal lactate but persistent acidosis may indicate another mechanism, such as renal dysfunction or hyperchloremia. This type of interpretive flexibility is part of good critical care practice.
Ultimately, the anion gap should inform, not replace, clinical judgment. It is best viewed as a dynamic marker that reflects changing physiology during resuscitation, especially when paired with serial laboratory values and hemodynamic monitoring.
When to Recheck Labs and Escalate Care
In shock, lab re-evaluation should be guided by the patient’s condition and the response to treatment. If there is ongoing hemodynamic instability, worsening acidosis, or concern for inadequate perfusion, repeat labs are appropriate. Rechecking the anion gap, bicarbonate, lactate, and related electrolytes helps determine whether resuscitation is working.
Lactate trend is especially useful. A decreasing lactate generally suggests restored perfusion and better oxygen delivery, while a continuously high or rising lactate can signal unresolved shock, ongoing ischemia, or a missed diagnosis. The anion gap often moves in parallel, though not perfectly, so trend analysis should include both.
Escalation to critical care is needed when the clinical picture shows progressive organ dysfunction, increasing vasopressor requirements, refractory acidosis, or concern for toxic alcohols, sepsis, or ischemia. The combination of high anion gap metabolic acidosis, rising lactate, and worsening hemodynamics https://anion-gap-formula708.bearsfanteamshop.com/how-to-calculate-the-delta-gap-using-an-anion-gap-calculator should trigger urgent reassessment of source control, perfusion, and underlying cause.
Practical monitoring often includes serial serum chemistry panels, repeat blood gas testing, and careful bedside reassessment after fluids, vasopressors, or other interventions. The goal is not to target a single target, but to verify that resuscitation is restoring perfusion and reversing the metabolic consequences of shock.
Frequently Asked Questions
What does the anion gap mean in shock?
The anion gap in shock is a calculated laboratory value that helps identify metabolic acidosis caused by unmeasured acids, most often lactate. When shock is present, it can be a helpful sign that tissue hypoperfusion is limiting oxygen delivery and promoting anaerobic metabolism. It should be read together with blood pressure, lactate, blood gas findings, and the broader clinical picture.
Why is the anion gap elevated in shock?
Shock can cause a high anion gap because poor perfusion leads to lactate rise and a lactic acid buildup. When tissues do not receive adequate oxygen, they produce additional acid through oxygen-free metabolism. Sepsis, ischemia, and severe hemodynamic instability can all lead to this finding.
Can shock occur with a normal anion gap?
Yes. Shock can happen with a regular anion gap, especially in initial shock or when the patient has hyperchloremic metabolic acidosis from hyperchloremia or fluid administration. A normal gap does not rule out serious hypoperfusion, so arterial blood gas results, lactate, and clinical assessment are essential.
How does albumin affect the anion gap?
Albumin level is a major unmeasured anion, so reduced albumin can depress the calculated anion gap and make a true acid-base disorder look harder to see. That is why albumin correction is essential. The corrected anion gap may reveal a hidden high anion gap metabolic acidosis in critically ill patients.
How often should the anion gap and lactate be rechecked in shock?
The timing depends on the seriousness of the illness and the answer to emergency treatment. In unstable patients, repeat labs are often required after therapy adjustments and at set intervals to follow the lactate trend and electrolyte changes. In intensive care, the aim is serial assessment until perfusion improves and the metabolic abnormalities begin to resolve.