An anion gap calculator can help you convert routine electrolyte values into a fast, clinically helpful snapshot of acid-base balance. By using common blood test results such as sodium, chloride, and bicarbonate, the calculator determines the anion gap, which can support interpretation of a serum chemistry panel and inform next steps in workup.
The value is not a diagnosis by itself. It is a diagnostic aid that helps spot patterns such as metabolic acidosis, including high anion gap metabolic acidosis and normal anion gap metabolic acidosis. The result becomes more informative when you consider serum albumin, the reference range, and the overall clinical context.
What the Anion Gap Calculator Measures
The anion gap is a derived value that indicates the relationship between measured positive and negatively charged particles in the blood. It is based on electrolytes commonly included on an electrolyte panel, especially sodium, chloride, and bicarbonate.
This measurement is based on electrical neutrality: your body preserves total positive and negative charges in balance. Because routine lab tests do not measure every ion in the blood, the anion gap approximates the amount of unmeasured ions. So it becomes a practical way to detect shifts in anion concentration that may signal an acid-base disorder.
In practice, the anion gap is often reviewed as part of a serum chemistry panel. A clinician may apply it to help interpret a lab result when symptoms, a blood gas, or other findings suggest an underlying metabolic problem. It is especially helpful when screening for causes of acidosis or identifying patterns that need additional testing.
Anion Gap Formula and Calculator Inputs
An anion gap calculator typically requires three main inputs: sodium, chloride, and bicarbonate. They are the core inputs used in the standard anion gap formula.
The most common formula is:
Anion gap = sodium - (chloride + bicarbonate)
Some calculators may also include a version that includes potassium, but the sodium-based formula is the one most commonly used for everyday interpretation. The exact formula depends on the lab or tool, so it is important to verify the measurement method before interpreting the result.
This is what each input represents:
- Sodium: the main measured cation in the body Chloride: the main measured anion that often shifts in the reverse direction of bicarbonate Bicarbonate: a key buffer that helps maintain pH balance
These values are usually reported in the same units on a blood test, which makes the calculation simple. The calculator performs the formula rapidly, but the real value comes from correct interpretation of the result.
How to Compute Anion Gap Using Electrolyte Values
The steps for calculation are easy, but getting it right matters. To begin, identify the relevant test values on the serum chemistry report. Then follow the formula using the sodium, chloride, and bicarbonate values.
Step-by-step:
- Identify the sodium value Locate the chloride value Find the bicarbonate value Add chloride and bicarbonate together Deduct that sum from sodium
Example calculation: If sodium is 140, chloride is 104, and bicarbonate is 24, the formula becomes 140 - (104 + 24). The result is 12. That number falls inside the usual reference range for many labs.
Although the math is straightforward, the interpretation depends on the lab's reference range. Different laboratories may report slightly different normal ranges because of differences in methodology and measurement. A value that is normal in one setting may be borderline in another.
It also helps to think of the result as part of a broader pattern rather than a stand-alone number. A normal result does not automatically rule out disease, and a high value does not identify the cause by itself. The anion gap is most useful when paired with the rest of the clinical picture.
Understanding a High Anion Gap Indicates
A elevated reading on an anion gap calculator often indicates that additional acids are present in the blood. This result is classically associated with acid buildup, especially high anion gap metabolic acidosis.
Frequent causes include excess lactic acid, ketoacidosis, uremia, and certain toxic substances. All of these conditions increases the amount of unmeasured anions, which increases the calculated gap.
Lactic acidosis can develop when tissues are not getting enough oxygen or when lactate production exceeds clearance. Ketoacidosis occurs when the body produces excess ketones, often in the setting of uncontrolled diabetes, starvation, or heavy alcohol use. Uremia reflects the accumulation of acids in advanced kidney failure. Toxins such as methanol, ethylene glycol, or salicylates can also cause a high anion gap.
A high result is a clue, not a final answer. The key question is why the acid imbalance is present. That is why clinicians often combine the anion gap with blood gas testing, kidney function, lactate, ketones, and toxicology when indicated.
What exactly is a Normal or Reduced Anion Gap Indicates
A result in the normal range does not always mean all is well. In some situations, a normal result may occur even when an acid-base imbalance is present, especially in normal anion gap metabolic acidosis.
Normal anion gap metabolic acidosis often stems from bicarbonate loss or chloride gain rather than the buildup of unmeasured acids. This pattern can be seen with diarrhea, renal tubular disorders, or certain fluid shifts. In these cases, the anion gap may stay within the expected reference range even though acid-base balance is disrupted.
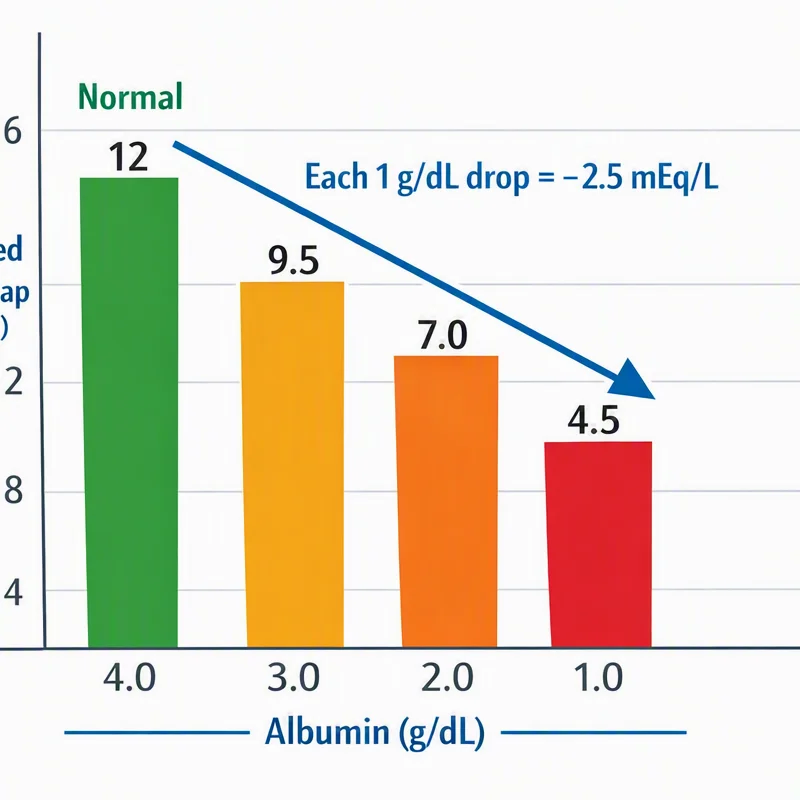
A low value can also be meaningful. One major cause is hypoalbuminemia, because albumin is an major unmeasured anion. When albumin falls, the calculated gap may fall even if other problems are present. Other causes include laboratory error and paraproteinemia, such as in plasma cell disorders, anion gap clinical significance where abnormal proteins can affect assessment.
If the result seems lower than expected, it is wise to recheck the measurement and review the broader clinical significance. Sometimes the issue is a transcription or sampling problem rather than a true physiologic change.
In What Way Albumin Adjustment Changes the Calculation
Serum albumin has got a major effect on the anion gap because albumin holds negative charge in the blood. When albumin is low, the measured gap may underestimate the presence of unmeasured acids. That is why clinicians often rely on an albumin correction or calculate an albumin-corrected anion gap.
The most common correction formula adjusts the gap upward when serum albumin is below normal. A typical approach is to include a correction factor for each decrease in albumin from the standard baseline. Different sources may use slightly different versions, so it is important to know which formula your calculator uses.
This correction strengthens interpretation because a patient with hypoalbuminemia may have a seemingly normal or low anion gap even while a metabolic problem is present. In that setting, albumin correction can reveal a hidden high anion gap and alter the clinical impression.
For practical use, always review the albumin level alongside the chemistry panel. A corrected result is not just a mathematical adjustment; it shifts the way the data fit the patient’s overall status. That is especially important when interpreting acidosis in hospitalized or critically ill patients.
Typical Clinical Applications of the Anion Gap
The anion gap is commonly used across acid-base disorders because it gives a quick way to screen for chemical problems. It is a routine tool in emergency medicine, where prompt decisions often depend on identifying the cause of acidosis. It is also common in critical care, where patients may have multiple overlapping metabolic abnormalities.
In kidney disease, the gap may elevate as acids accumulate and clearance declines. This makes the calculation useful for assessing worsening metabolic status and recognizing complications that require urgent attention.
Other common uses include evaluating unexplained illness, checking whether a blood test pattern suggests lactic acidosis or ketoacidosis, and helping distinguish between different causes of metabolic acidosis. The test works best as a screening and interpretation tool rather than a final diagnosis.
Because it is simple to calculate from routine electrolyte values, the anion gap is often one of the first numbers reviewed after a chemistry panel. Its swiftness and simplicity are part of what makes it so clinically useful.
Drawbacks of an Anion Gap Calculator
An anion gap calculator is only as reliable as the data entered into it. The result depends on the reference range used by the lab, the measurement method, and the quality of the input values. Even small differences in sodium, chloride, or bicarbonate can change the output.
One important technical issue is the use of an ion-selective electrode. This common method for measuring electrolytes can produce results that differ slightly from other methods, which affects the calculated gap. That is one reason different labs may report different normal ranges.
Another limitation is that the calculator does not know the full clinical context. A number alone cannot tell you whether the patient has a mixed disorder, a sampling issue, or a condition that requires urgent treatment. The same result may have very different meaning depending on symptoms, history, and other laboratory findings.
To get the best use, treat the calculator as a useful starting point. It can determine the gap rapidly, but interpretation should always include albumin, acid-base status, and the rest of the blood test results.
Frequently Asked Questions
How do you calculate the anion gap from electrolyte values?
Apply the standard anion gap formula: sodium minus the sum of chloride and bicarbonate. In simple terms, anion gap = sodium - (chloride + bicarbonate). Enter the three electrolyte values into an anion gap calculator, and it will determine the result automatically. The answer should then be interpreted in the setting of the lab’s reference range and the patient’s clinical picture.
What is a normal anion gap range?
The normal range changes by laboratory because of differences in the measurement method and reporting standards. Many labs use a range that is roughly 8 to 12, but the exact reference range should always come from the specific lab report. A normal result does not rule out every acid-base disorder, especially normal anion gap metabolic acidosis.
What causes a high anion gap?
A high anion gap usually means there are extra unmeasured acids in the blood. Common causes include lactic acidosis, ketoacidosis, uremia, and toxins. These conditions are classic causes of high anion gap metabolic acidosis. The result should be interpreted with symptoms, other lab tests, and overall patient context.
Why does low albumin affect the anion gap?
Albumin is a major unmeasured anion, so when serum albumin is low, the calculated gap may fall even if acids are present. This is why hypoalbuminemia can hide a clinically important problem. Using an albumin correction or an albumin-corrected anion gap helps improve interpretation and may reveal a masked high gap.
When should an anion gap result be evaluated with relevant lab tests?
It should always be reviewed with complementary tests when the result is outside the normal range or when symptoms point to a metabolic problem. The anion gap is most useful alongside bicarbonate, blood gas results, kidney function, lactate, ketones, and occasionally toxicology. Because the number https://anion-gap-guide487.theburnward.com/what-is-bicarbonate-s-role-in-the-anion-gap is a screening test, its clinical significance depends on the broader serum chemistry panel and the overall acid-base balance picture.