How the Anion Gap Is Measured
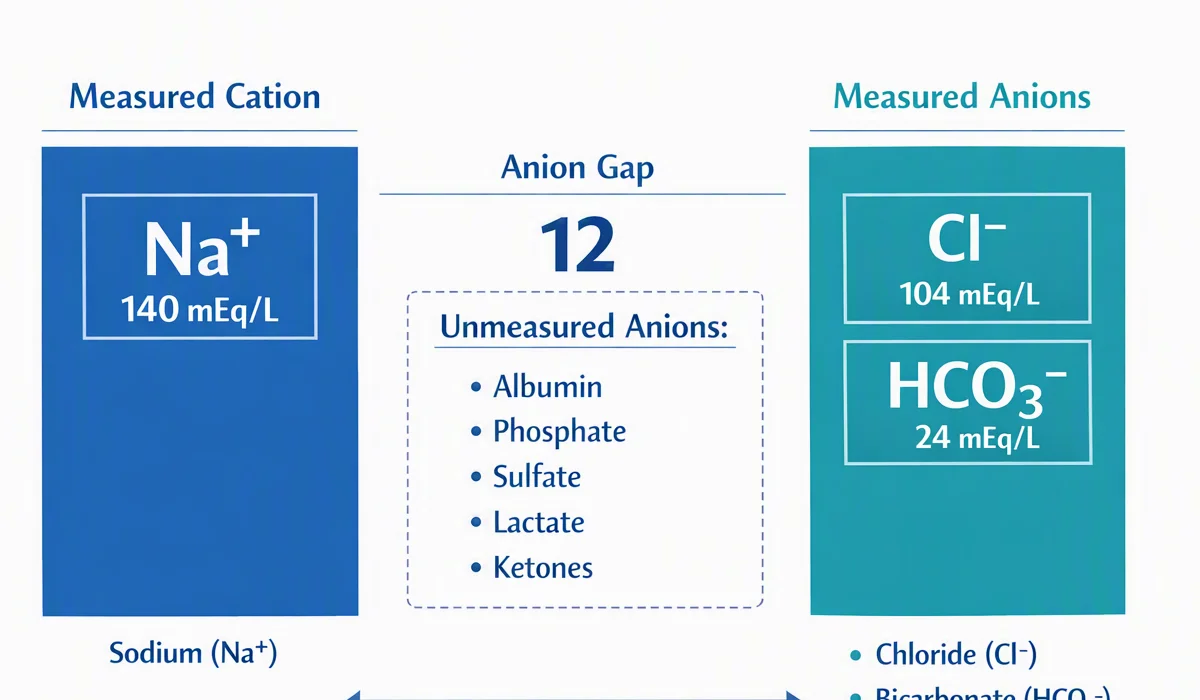
The anion gap is a derived value that helps evaluate an electrolyte panel and detect certain acid-base disorder patterns. It compares the main positively charged and negative particles in serum electrolytes, especially sodium, chloride, and bicarbonate. Because routine chemistry tests do not measure every charged particle in the blood, the anion gap approximates the difference between measured cations and measured anions.
In clinical terms, a low, normal, or elevated anion gap can be a useful diagnostic clue during blood test interpretation. A high value often raises concern for metabolic acidosis, while a low anion gap indicates a different set of possibilities such as hypoalbuminemia, laboratory issues, or excess unmeasured positive ions. The result should always be read alongside the rest of the serum chemistry panel and the patient’s symptoms.
The exact formula used for anion gap calculation anion gap clinical significance may differ by laboratory, but it usually relies on sodium, chloride, and bicarbonate. Because these components are part of standard chemistry testing, the anion gap is not a direct measurement. It is a calculated number that reflects acid-base balance and broader electrolyte imbalance patterns.
How an Anion Gap Calculator Functions
A Anion Gap Calculator applies the calculation method chosen by the specific laboratory to estimate the gap from sodium, chloride, and bicarbonate values. Numerous calculators also offer albumin correction, which is significant because albumin is a major unmeasured anion in blood. When albumin is low, the displayed anion gap may be spuriously decreased, and a corrected anion gap can more reliably reflect the true picture.
The usual calculator presents the result and compares it with the laboratory reference range. That range varies a little from one lab to another because different analyzers and methods can alter the expected values. For that reason, the same number may be interpreted differently depending on the lab’s reporting standards.
Using an Anion Gap Calculator is valuable when you want a rapid, systematic look at a lab result, but the number should not be interpreted in isolation. If bicarbonate is low, for example, the result may point to metabolic acidosis. If bicarbonate is high, the picture may suggest metabolic alkalosis. The calculator is a tool for lab result interpretation, not a diagnosis by itself.
Some calculators also help users think through the cause of low anion gap findings by prompting consideration of albumin, calcium, and other ions. This is especially helpful when the result seems surprising or when there is an unexplained result that does not fit the clinical picture.
Can Hypercalcemia Lower the Anion Gap?
Absolutely, hypercalcemia can reduce the anion gap, but it usually does so only modestly. The reason is that elevated serum calcium boosts the amount of circulating positive charge from calcium ions, which can reduce the calculated gap between measured cations and measured anions. In theory, this shifts the balance of electrolyte balance and may result in a decreased anion gap.
However, the effect is often minor and not the most common explanation for a low result. In real-world practice, a low anion gap is much more likely to reflect hypoalbuminemia or another issue than to be caused primarily by hypercalcemia. This is why hypercalcemia is best viewed as one possible contributor rather than the leading cause of low anion gap.
The influence of calcium also depends on other factors such as the patient’s albumin level, kidney status, and whether there is another acid-base abnormality present. Because albumin carries a substantial negative charge through protein binding, a low albumin concentration can obscure or amplify the impact of calcium on the final number. In other words, the same calcium level may matter more or less depending on the surrounding chemistry.
From a practical standpoint, if a patient has both hypercalcemia and a low anion gap, the result should not automatically be attributed to calcium alone. The broader differential diagnosis should still include albumin deficiency, paraproteins, medications, and lab-related issues. Hypercalcemia may be part of the story, but it is usually not the whole story.
The Reason Hypercalcemia Usually Has a Small Effect
To understand why hypercalcemia typically has a modest effect, it helps to think in terms of measured cations and unmeasured anions. The anion gap is designed to measure the gap left by ions that are not directly measured on a routine panel. Sodium is the major measured cation, while chloride and bicarbonate are measured anions. Calcium is not always included in the standard calculation, so changes in calcium can influence the balance without dominating it.
Most of the time, the body also responds through physiologic compensation. Shifts in renal handling, bicarbonate balance, and other electrolytes can partially offset changes in calcium-related charge distribution. That buffering effect helps explain why even marked hypercalcemia does not usually create a dramatic low anion gap on its own.
Another practical limitation is laboratory variation. Small differences in analyzer methods, specimen handling, or reporting conventions can produce changes that are comparable in size to the effect of calcium itself. As a result, a slight decrease in the anion gap may reflect ordinary variation rather than a meaningful physiologic change.
This is why a low value should be interpreted carefully. If the result is only mildly below the reference range, hypercalcemia may be a contributing factor, but the number may not have major clinical significance by itself. If the decrease is substantial, another explanation is usually present and should be investigated.
Other Sources of a Low Anion Gap
When a low anion gap appears, hypoalbuminemia is one of the first reasons to consider. Albumin is a major unmeasured anion, so low levels often reduce the gap more than any other common factor. This is why albumin should always be measured when interpreting an unexpected result.
Paraproteinemia, including conditions such as multiple myeloma, is another important cause. Abnormal positively charged proteins can function as unmeasured cations and lower the gap. In this setting, the low anion gap may be an early clue that points toward a plasma cell disorder rather than a simple electrolyte issue.
Medication and toxin effects can also matter. Lithium toxicity can produce a low anion gap because lithium acts as an unmeasured cation. Bromide interference is another classic reason, since bromide may be misread by some assays as chloride, causing chloride to appear artificially high and the gap to appear lower than it really is.
These causes are generally more common and more clinically important than mild hypercalcemia. That does not mean calcium is irrelevant, but it does mean that a truly low anion gap should prompt a broader review of the electrolyte panel, medications, protein status, and possible assay issues.
When to Suspect a Lab Artifact
A low anion gap should suggest the chance of a laboratory artifact before it is viewed as a actual physiologic finding. Because the calculation rests on several measured values, even a slight error in sodium, chloride, or bicarbonate can alter the final result. If the number does not fit the patient’s condition, measurement accuracy should be checked.
Repeat testing is often the starting step. A fresh specimen can help confirm whether the result was due to sample error, collection problems, contamination, or a transient analytical issue. Repeating the chemistry panel is especially valuable when the low anion gap is surprising or when other values seem off.
Interference from substances such as bromide, lithium, or other analytes can also cause misleading Extra resources results. In some cases, the analyzer may incorrectly read chloride or sodium, causing a false low anion gap. This is why clinicians often review the entire lab pattern, not just the final calculated number.
If the finding persists on repeat lab test, then the result is more likely to be legitimate and clinically relevant. At that point, the next step is usually a more thorough metabolic evaluation, including albumin, calcium, kidney testing, and assessment for paraproteins or medication effects.
How to Understand the Result in Context
A helpful way to understand a low anion gap is to view it in clinical context. The result alone does not diagnose an acid-base disorder; it simply fits into the overall assessment. For example, a low anion gap with low bicarbonate may suggest a mixed disorder, while a low anion gap with normal bicarbonate may be more consistent with hypoalbuminemia or paraproteinemia.
It is also important to watch for signs of metabolic acidosis or metabolic alkalosis. A high or low bicarbonate level alters the interpretation of the full electrolyte pattern. When bicarbonate is abnormal, the anion gap may aid in identifying whether the disturbance is part of a more extensive acid-base balance problem or whether it is a separate issue.
Renal function is important as well. Kidney disease can change bicarbonate handling, influence unmeasured ions, and alter how the body compensates for acid-base shifts. A patient with impaired renal function may show a different pattern than someone with normal kidney function even when the same serum calcium level is present.
In real-world use, the best approach is to combine the number from an Anion Gap Calculator with symptoms, the rest of the electrolyte panel, and any relevant medical history. That helps separate a true physiologic change from a minor variation with little clinical significance.
When It Is Time for Medical Evaluation
A medical assessment is recommended when a low anion gap appears alongside symptoms of hypercalcemia or other concerning findings. These symptoms can include increased thirst, frequent urination, constipation, nausea, confusion, weakness, or fatigue. When symptoms are present, the chemistry result may indicate a clinically meaningful electrolyte imbalance rather than a benign variation.
Evaluation is also more pressing when there are severe electrolyte abnormalities, especially if multiple values on the electrolyte panel are abnormal at the same time. A markedly abnormal calcium level, major bicarbonate shift, or unusual chloride pattern should not be dismissed.
ECG changes add another layer of risk. Hypercalcemia can affect cardiac conduction, and abnormal cardiac findings increase the need for prompt medical review. If the low anion gap occurs in the setting of heart rhythm symptoms, syncope, or chest discomfort, the situation deserves urgent attention.
In general, a medical professional should evaluate persistent or unexplained low anion gap findings, especially if albumin is normal and repeat lab test confirmation shows the same pattern. The goal is to determine whether the result reflects hypercalcemia, a protein abnormality, a medication effect, kidney disease, or another metabolic evaluation issue that needs additional review.
FAQ
Can hypercalcemia lower the anion gap?
Yes, it can. Hypercalcemia can lower the anion gap because calcium acts as a cation that can shift electrolyte balance. However, the effect is usually small, and a low anion gap is more often caused by hypoalbuminemia, paraproteinemia, or lab-related issues than by calcium alone.
How much can calcium change the anion gap?
Calcium usually changes the anion gap only modestly. A noticeably low result is rarely explained by calcium alone. If the change seems large, consider albumin, unmeasured cations, measurement error, or another acid-base disorder rather than assuming hypercalcemia is the only cause.
What is the leading cause of a low anion gap?
The most common reason is hypoalbuminemia. Because albumin is a important unmeasured anion, low albumin often lowers the anion gap more than any other factor. This is why albumin correction is essential in lab result interpretation.
Should albumin be corrected when calculating the anion gap?
Absolutely, when albumin is low or when the result is unexpectedly decreased, albumin correction is often helpful. A corrected anion gap can provide a more reliable view of acid-base balance and can prevent a false impression that the gap is truly low.
When does a low anion gap need further evaluation?
A low anion gap needs further evaluation when it is ongoing, not explained, or accompanied by symptoms, severe electrolyte abnormalities, or abnormal kidney function. It should also be evaluated if there is concern for paraproteinemia, multiple myeloma, lithium toxicity, bromide interference, or a possible laboratory artifact.