What’s the Anion Gap?
The anion gap is a basic but valuable value derived from routine electrolytes on a serum chemistry panel. It assists clinicians in identifying hidden acids or other unmeasured anions that may be affecting a patient’s chemistry. In practical terms, the anion gap value supports clinical interpretation of blood chemistry by showing whether there may be an underlying electrolyte imbalance or metabolic acid-base disorder.
The classic anion gap formula compares positively charged ions with negatively charged ions, most commonly using serum sodium, serum chloride, and serum bicarbonate. In many lab systems, potassium may also be included, although the most common version excludes it. The result is not a direct measurement of acid, but a diagnostic aid that can suggest conditions that require more detailed acid-base evaluation.
Because the anion gap is calculated from standard laboratory results, it is widely used in bedside and outpatient patient assessment. A careful review of the number can suggest whether there is a high anion gap pattern, a normal anion gap state, or an unexpectedly low anion gap that deserves confirmation.
How Refined Anion Gap Counts
The typical anion gap is helpful, but it can be misleading when albumin is low. Since serum albumin holds a substantial amount of negative electrical charge in the blood, hypoalbuminemia can reduce the measured gap even when relevant acids are present. That is why the corrected anion gap is important: it calibrates the number so the clinician can more effectively evaluate acid-base balance.
In the absence of albumin adjustment, a patient with significant metabolic acidosis may seem to have a comforting result. That is especially important in hospitalized or critically ill patients, where albumin may decline because of inflammation, poor nutrition, fluid shifts, or illness severity. In these situations, the corrected value strengthens diagnostic interpretation and supports more accurate decisions.
The corrected result is not meant to substitute for clinical judgment. Instead, it adds context to the raw calculation and improves clinical significance. For example, a “normal” anion gap in a patient with low albumin may still mask a true acid load. That is why correction is often a truer reflection of real physiology than the unadjusted number alone.
How the Anion Gap Calculator Operates
The Anion Gap Calculator simplifies the anion gap calculation so clinicians and students can quickly calculate the gap from everyday blood chemistry. Most calculators rely on a simple calculation formula based on serum sodium, serum chloride, and serum bicarbonate. In its common form, the calculation is:
Some versions also incorporate potassium, which somewhat changes the result. A potassium-inclusive formula may be written as:
anion gap = sodium + potassium - (chloride + bicarbonate)Both versions are used in practice, but the sodium-based formula is the anion gap clinical significance most familiar. The calculator does not diagnose disease by itself; it is a diagnostic aid that helps assess the broader pattern of blood chemistry. When paired with the patient’s clinical signs, pH, lactate, ketones, kidney function, and medication history, it becomes part of a comprehensive clinical interpretation.
Because the anion gap shows the difference between measured cations and measured anions, it indirectly indicates the presence of unmeasured anions. That is why it is so useful in detecting metabolic problems that might otherwise be overlooked on a standard serum chemistry panel.
Calculating the Anion Gap for Albumin
The adjusted gap reflects the impact of albumin in the blood. Because albumin is a key negatively charged protein, decreased levels can make the gap seem falsely low or normal. The correction for albumin updates the number upward when albumin is below the normal reference interval.
A common correction approach applies a fixed amount for each gram per deciliter that albumin is below normal. Various institutions may use slightly different formulas, so the exact adjustment may vary. In general, the lower the albumin, the greater the need for recalculation. This is the practical heart of anion gap adjustment.
Why does this matter so much? Because hypoalbuminemia can mask a true acid imbalance. A patient may have a standard anion gap that looks unremarkable, yet the corrected value reveals a clinically significant elevation. That difference can change the workup, the urgency of treatment, and the interpretation of the overall acid-base state.
Reviewing the corrected result is very important when comparing values against a lab’s reference interval. A “normal” uncorrected number may no longer be normal after albumin correction. For this reason, the corrected calculation is often a better reflection of the patient’s true clinical significance than the raw value alone.
Common Causes of an Elevated Anion Gap
An increased gap commonly suggests presence of acid compounds or unmeasured negative ions. The most common causes include lactate acidosis, ketone acidosis, kidney failure, and certain poisonous ingestions. These states can all disturb the acid-base balance and show a clear increased anion gap pattern.
Elevated lactate can occur when tissues are not adequately perfused or under metabolic stress, leading to excess lactate production. Ketoacidosis develops when ketone bodies accumulate, often in diabetes, alcohol-related illness, or prolonged fasting. Kidney failure can increase the gap because the kidneys are unable to clear acids effectively.
Toxic alcohols are another major cause of increased values. Ingestions involving methanol, ethylene glycol, and related compounds can produce major acid-base derangements that may be life-threatening. Salicylates can also alter the pattern, sometimes creating a mixed disorder that requires careful review of the full clinical picture.
Because these disorders can overlap, the anion gap should be viewed as one piece of the puzzle. It supports clinical interpretation, but it does not replace history, exam, medication review, and targeted testing. The calculator is most useful when it helps determine the following step in the diagnostic process.
How to Understand Normal or Low Anion Gap Results
A low anion gap is rarer than an elevated one, but it can still have significance. Before assuming disease, the first question is whether the result is genuine. Laboratory error is one of the most frequent explanations, so rerunning the test is often the first step if the result is unanticipated.
A within-range anion gap does not always mean there is no acid-base disorder. If the patient has hypoalbuminemia, the true gap may be too low until an albumin correction is applied. That is why the adjusted result can be more helpful than the initial number when considering metabolic acidosis.
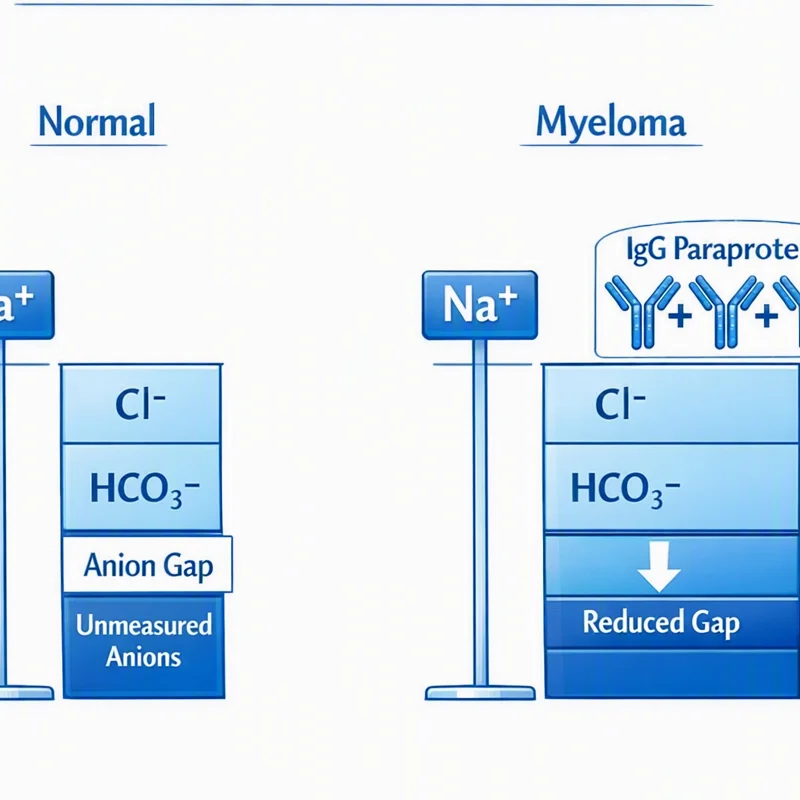
Another important cause of a decreased or unexpectedly average result is paraproteinemia. Abnormal proteins can change the blood chemistry pattern and affect the apparent balance of measured ions. In such cases, the anion gap is not a diagnosis by itself, but a hint that may prompt further workup.
When evaluating low or normal results, look at the entire clinical interpretation: albumin level, other https://anion-gap-reference419.talesignal.com/posts/anion-gap-calculator-for-evaluating-acidemia electrolytes, pH, bicarbonate, kidney function, and the patient’s symptoms. This broader approach improves diagnostic interpretation and helps prevent false reassurance.
Detailed Sample Calculation
Here is a basic worked example with standard laboratory values. Suppose the patient has the following:
- serum sodium: 140 blood chloride: 102 serum bicarbonate: 18 blood potassium: 4.0
Using the common sodium-based formula, the calculation is:
anion gap = 140 - (102 + 18)That gives an anion gap of 20. Provided that the lab’s expected range is lower than that, this may indicate a increased anion gap. When the patient also has low serum albumin, the next step is adjusting for albumin to determine the albumin-corrected anion gap.
Next assume the albumin is reduced. Once applying the appropriate anion gap correction, the corrected value may be even higher, revealing a more significant metabolic problem than the unadjusted number suggested. For this reason the Anion Gap Calculator is a highly practical assessment tool: it simplifies the math while preserving the clinical meaning.
This worked example also shows how the result connects to the rest of the evaluation. A high gap with low bicarbonate can support concern for acid-base imbalance, while the underlying cause may be lactic acidosis, ketone-related acidosis, renal insufficiency, toxic alcohols, or aspirin-related compounds. The calculator does not identify the cause, but it assists in narrowing the differential.
Frequently Asked Questions About Corrected Anion Gap Results
What exactly is a corrected anion gap and why is it used?
The corrected anion gap is the standard anion gap modified for low serum albumin. It is used because hypoalbuminemia can make the uncorrected value look misleadingly normal. The correction strengthens clinical interpretation and more accurately shows the patient’s true acid-base balance.
How do you calculate the anion gap with albumin correction?
Start with the usual anion gap formula using serum sodium, serum chloride, and serum bicarbonate. Then add an albumin correction based on the measured serum albumin. The exact method may change by institution, so the calculator should follow the same reference range and formula used by the lab or clinical setting.
What can indicate a high anion gap?
A high anion gap commonly suggests extra acids in the blood, such as in lactic acidosis, ketoacidosis, renal failure, or exposure to toxic alcohols or salicylates. It is a key clue in the evaluation of metabolic acidosis, but it should be interpreted with the rest of the laboratory results and the patient’s symptoms.
Can a normal anion gap still mean a serious problem?
Yes. A normal anion gap does not always rule out clinically important illness. Hypoalbuminemia can hide a true gap, and a lab error can also distort the result. In addition, a patient may have another type of metabolic problem that requires broader acid-base evaluation and clinical review.
When should an anion gap result be reviewed by a clinician?
Any unexpected result should be reviewed when it does not fit the patient’s condition, especially if there is metabolic acidosis, altered mental status, kidney dysfunction, suspected poisoning, or significant electrolyte imbalance. The result is best used as a diagnostic aid within overall patient assessment, not as a standalone answer.