What Is the Anion Gap?
The anion gap is a calculated value used in a blood test to assess the balance of electrolytes in the body. It is typically obtained from the main measured ions in a serum chemistry panel: sodium, chloride, and bicarbonate. Because not every charged particle is directly measured, the anion gap helps determine the difference between measured cations and unmeasured anions.
In simple terms, the anion gap is a useful diagnostic tool for assessing acid-base balance. A normal result points to a narrower range of likely causes, while a low anion gap or high anion gap can suggest different types of acid-base disorder. Clinicians often use an electrolyte panel or broader serum chemistry to calculate it as part of a metabolic evaluation.
The most common formula is:
Anion gap = Sodium - (Chloride + Bicarbonate)
Because the result depends heavily on the sodium concentration, any condition that changes sodium can alter the calculation. That is why sodium, chloride, and bicarbonate level are key to understanding the result.
What Is Hyponatremia?
Hyponatremia means a low serum sodium level. It’s one of the commonest electrolyte abnormalities encountered in practice and usually indicates an shift in water balance rather than a true loss of sodium alone. In many instances, the body has too much water relative to sodium, which lowers the measured concentration.
To understand hyponatremia, clinicians also consider osmolality, which reflects the concentration of dissolved particles in blood. The interaction of serum sodium and osmolality helps clarify whether the sodium abnormality is due to excess water, true sodium loss, or some other mechanism. This matters because a low sodium value may be part of a broader electrolyte imbalance or a separate issue that does not directly change the anion gap.
Hyponatremia can be associated with many different conditions, including fluid shifts, hormonal problems, medications, and severe illness. The key point is that the low sodium itself does not automatically mean there is an acid-base disorder. It may coexist with one, but the association is not guaranteed.
Can Sodium deficiency Affect the Anion Gap?
Yes, low sodium can change the anion gap because sodium is used in the calculation. If the sodium value falls while chloride and bicarbonate remain stable, the calculated gap may fall. That said, the effect depends on the general pattern of lab interpretation and not just the sodium number alone.
Using an anion gap calculator can help show how changes in serum sodium influence the result. Still, a low sodium level does not always create a truly abnormal gap in a clinically meaningful way. Sometimes, the value changes on paper because of the math, while the underlying acid-base status remains balanced.
This is why, the anion gap should never be interpreted in isolation. A person may have low sodium from a dilutional process, yet the gap may still be normal after considering the rest of the serum electrolytes. In some situations, a low sodium value may accompany disorders that also lower bicarbonate or shift chloride, leading to a more significant change in the gap.
Clinical clinical interpretation depends on the full pattern of laboratory values, symptoms, and the suspected diagnosis. The anion gap is an important clue, not the final answer.
How Sodium Levels Shape the Result
The anion gap formula is immediately affected by sodium concentration because sodium is the first value in the calculation. When sodium decreases, the numerical gap usually decreases as well, assuming chloride and bicarbonate are kept similar. This is a straightforward math effect, but the body’s chemistry is far more complex than the formula alone suggests.
Bicarbonate and chloride shift can influence the result in opposite ways. For example, if bicarbonate is low because of metabolic acidosis, the anion gap may rise if the fall in bicarbonate is not matched by a corresponding rise in chloride. On the other hand, if chloride increases to make up for it, the gap may appear normal even though an acid-base problem exists.
Albumin also is important because it is a major unmeasured anion. Lower albumin lowers the anion gap even when the sodium level is stable. So in a patient with hyponatremia, a low gap may suggest both the sodium change and the effect of albumin. This is why a simple calculation can be deceptive without considering the rest of the blood chemistry.
In practice, serum anion gap calculator the lab math works best when viewed as part of the full acid-base balance picture. Sodium does affect the number, but it is only one component of the broader interpretation.
When a Low Anion Gap Is Observed
A low anion gap is less common than a high one, and it often needs careful review. One major cause is hypoalbuminemia, since albumin is a major unmeasured anion. When albumin falls, the gap often falls as well, even without a major change in the underlying acid-base state.
Testing error is another important possibility. Mistakes in specimen handling, measurement, or reporting can create a falsely low result. If the number does not fit the clinical picture, repeat testing is often necessary before drawing conclusions.
Paraproteinemia can also reduce the anion gap. Abnormal proteins may behave as unmeasured cations or alter the electrochemical balance in ways that lower the calculated gap. This is especially relevant when the patient has other findings that suggest a plasma cell disorder.
In some cases, unmeasured cations such as lithium or marked increases in other positively charged substances can reduce the calculated gap. That is why a low result should prompt review of medications, the overall electrolyte panel, and the broader clinical context.
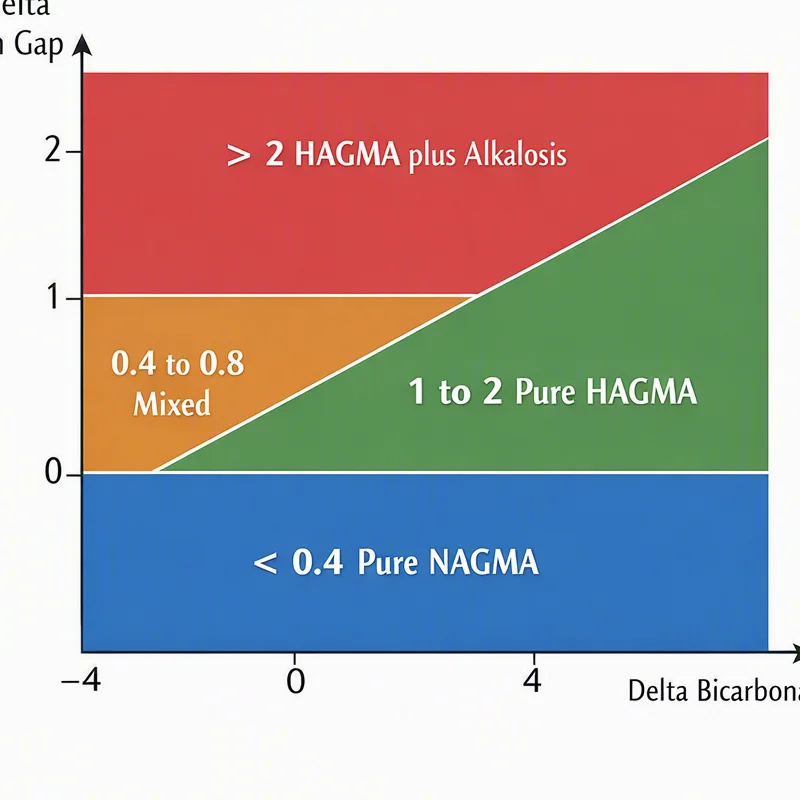
Adjusting the Anion Gap
Since albumin greatly influences the calculation, clinicians often use an albumin correction to determine a more accurate adjusted anion gap. This adjustment serves account for the fact that low albumin can mask an elevated gap or make a normal gap appear low.
The expected range for the anion gap varies somewhat by laboratory method, so interpretation should always use the range reported with the patient’s laboratory values. A value that looks low in one setting may fall within another lab’s expected range. Method differences matter, particularly when comparing results across systems.
Correcting for albumin is especially useful when evaluating possible acid-base disturbance. For example, a patient with low albumin and a “normal” gap may still have an elevated corrected gap that more accurately reflects hidden acid accumulation. In that situation, the correction can shift the direction of the clinical interpretation.
The goal is not to replace judgment with a formula, but to improve it. A corrected value provides a better estimate of the true acid-base picture and helps identify whether the apparent abnormality is driven by albumin, sodium, chloride, bicarbonate, or a combination of factors.
Using an Anion Gap Calculator
An anion gap calculator is useful because it quickly combines the main input values from serum electrolytes. By entering sodium, chloride, and bicarbonate, the calculator returns the calculated gap and often helps evaluate that value with the expected reference range. This is especially important when assessing complex clinical interpretation scenarios.
For patients with hyponatremia, the calculator can show whether the low sodium concentration is likely to have a major effect on the gap. It can also help reveal whether the result is better explained by hypoalbuminemia, a hidden high anion gap, or another abnormality in the lab pattern. In that sense, the calculator is a reliable diagnostic tool for bedside decision-making.
When working with the calculator, make sure the values come from the same specimen and same blood test. Mixed or delayed results can distort the calculation. A careful review of serum chemistry results, along with the patient’s symptoms and history, improves accuracy more anion gap clinical significance than the number alone.
The best use of an anion gap calculator is not just to produce a number, but to support a thoughtful interpretation of the overall metabolic picture.
What Else Needs To Be Checked?
When the anion gap is elevated or low, other tests often help clarify the cause. A blood gas can show pH and confirm whether there is an acid-base disorder. It also helps determine whether the patient has acidemia, alkalemia, or a mixed disturbance.
Serum bicarbonate should be checked closely because it is directly part of the calculation and a major clue to metabolic acidosis. If bicarbonate is low, the clinician should think about causes such as lactic acidosis, ketoacidosis, renal impairment, or toxin exposure.
Lactate is important when evaluating an elevated gap, especially if poor perfusion, infection, or tissue hypoxia is possible. Elevated lactate suggests accumulation of unmeasured acids and can explain a meaningful shift in the gap.
Ketones should also be checked when the clinical setting suggests ketoacidosis, starvation, or severe insulin deficiency. Ketone accumulation increases unmeasured anions and can significantly raise the anion gap. In a patient with hyponatremia, these additional tests help separate a true acid-base problem from a simple sodium imbalance.
Additional information may include kidney function, medication review, and assessment for toxin exposure. Together, these help determine whether the abnormal value reflects a transient laboratory issue or a real metabolic problem.
FAQ
Can hyponatremia lower the anion gap?
Yes, it can. Because sodium is part of the anion gap formula, hyponatremia can lower the calculated anion gap. However, the size of the effect depends on the full pattern of chloride, bicarbonate, and albumin. A low sodium value does not always mean the gap is clinically important.
Does a low sodium level always mean a low anion gap?
No, it does not. A low serum sodium does not automatically produce a low gap. The final result depends on the balance of electrolytes, including chloride and bicarbonate, as well as factors like hypoalbuminemia and lab method. Many cases of hyponatremia have a normal anion gap.
How should you calculate the anion gap for low albumin?
You use an albumin correction to determine the corrected anion gap. Since albumin is a important unmeasured anion, low albumin can make the gap look smaller than it really is. Correcting for albumin enhances clinical interpretation, especially when evaluating possible metabolic acidosis.
When ought a low anion gap be repeated or confirmed?
A low gap should be repeated when the result does not align with the patient’s condition or when lab error is possible. Confirmation is also reasonable if the value is unexpected, if the specimen quality is uncertain, or if there is concern for paraproteinemia or unmeasured cations. Repeating the test can help distinguish a real abnormality from a spurious one.
What other tests help interpret an abnormal anion gap?
Helpful tests include a blood gas, serum bicarbonate, lactate, and ketones. These studies help identify whether the abnormality is part of an acid-base disorder, such as metabolic acidosis, or whether it is more related to sodium changes, albumin changes, or another electrolyte imbalance.