Indeed, dehydration can impact the anion gap, but generally indirectly. The main issue is that fluid loss can change blood volume and cause concentration changes in lab values, which may lead to the result look different without necessarily meaning there is a serious metabolic problem. An Anion Gap Calculator can let you estimate the number, but clinical interpretation depends on the full picture, including the electrolyte panel, serum bicarbonate, albumin, and symptoms.
This difference matters. A changed result may reflect simple hemoconcentration from fluid loss, or it may point to a genuine acid-base issue such as metabolic acidosis. Knowing the difference helps you know when the result is likely temporary and when it needs a closer look.
What Is the Anion Gap?
The anion gap is a calculated figure used in blood chemistry to help evaluate acid-base balance. It is not a measured value. Instead, it indicates the gap between regularly measured charged particles, especially sodium and chloride, along with bicarbonate in many formulas. This makes it a helpful diagnostic marker for certain kinds of metabolic disorder.
Simply put, the anion gap helps clinicians look for unmeasured ions in the blood. If the gap is elevated, it can point to extra acids are present. If it is reduced, it may suggest low protein levels, lab issues, or reduced unmeasured positive ions than usual.
The precise reference range can vary depending on the lab and the method used. That is why clinical interpretation should always use the result from the same testing anion gap clinical significance facility or a trusted medical testing source rather than a one standard number.
The main components behind the calculation are part of routine serum electrolytes. Because these are commonly included in a basic metabolic panel or a broader electrolyte panel, the anion gap is often available even when it is not ordered as a separate test. That makes it a convenient tool for assessing blood chemistry and spotting abnormal results.
How an Anion Gap Calculator Operates
An anion gap calculator uses the numbers from a blood test to calculate the gap fast. Most calculators rely on sodium, chloride, and serum bicarbonate. Certain formulas also adjust for albumin, because albumin is a important unmeasured anion and can greatly influence the result.
The usual logic is clear: the calculator performs an anion calculation by contrasting the measured cations and anions in the sample. When bicarbonate is low, the gap often increases because bicarbonate is being depleted or lost while unmeasured acids accumulate. When albumin is low, the gap may seem lower than expected even if the true acid-base state is more complex.
This is why a calculator is valuable, but not sufficient. It provides a numeric estimate, not a diagnosis. The result must be interpreted alongside the electrolyte panel, the basic metabolic panel, and the patient’s overall condition. In plain terms, the calculator is best used as part of supportive assessment, not as a isolated answer.
Albumin deserves special attention. Because it carries negative charge, low albumin can reduce the measured gap. Several clinicians will consider a correction when hypoalbuminemia is present, since failing to account for it can hide a clinically important high anion gap.
Can Fluid loss Influence the Anion Gap?
Lack of fluids can change the anion gap, but the effect is often due to reduced body fluid and more concentrated blood rather than a direct change in acid production. When blood volume falls, some blood components become more concentrated. That can skew laboratory results on a blood draw and make results look more abnormal than they would after rehydration.
In slight dehydration, the anion gap may not change much at all. In more significant dehydration, especially when accompanied by vomiting, poor intake, or illness, the numbers can change enough to stand out. However, the key question is whether the change reflects simple salt imbalance or a true metabolic disturbance.
Lack of fluids alone does not usually cause a major raised anion gap. Instead, it may contribute to related problems that raise the gap, such as reduced kidney clearance, lactic acid buildup from poor perfusion, or ketone production if intake is very low. That is why a changed result should prompt the question: what is the root cause?
From a practical standpoint, dehydration can also make an already abnormal result look worse. A person with underlying illness may have borderline blood chemistry, and fluid loss can intensify the apparent abnormality. This is where careful clinical interpretation matters most.
Why Dehydration Might Change Lab Results
A major way dehydration affects testing is through hemoconcentration. As plasma water is reduced, measured substances in the blood can seem more concentrated. It can affect lab values across the test panel, including sodium, chloride, bicarbonate, and other markers on a basic metabolic panel.
An additional consideration is kidney function. The kidneys help balance water, electrolytes, and acid-base status. When dehydration reduces kidney perfusion, the body may briefly retain waste products and alter serum chemistry. That is why BUN and creatinine are often reviewed together. A raised BUN-to-creatinine pattern can suggest low fluid volume, though the overall context matters.
Dehydration can also be a clue that the body is under stress from illness, not just lacking water. As an example, vomiting, fever, diarrhea, or poor intake can lead to both fluid loss and metabolic changes. In those situations, the lab pattern may reflect more than simple dehydration, and the anion gap becomes one piece of a larger puzzle.
It can be useful to consider the result as part of an integrated review of blood chemistry. If BUN is elevated, creatinine is affected, and the anion gap is abnormal, the pattern may point toward dehydration-related strain on the kidneys or another process altogether. This is where a clinician compares the numbers with symptoms and exam findings.
When a Raised Anion Gap Is More Worrisome
A raised anion gap is more concerning when it suggests metabolic acidosis. In other words, acids are piling up in the body faster than they can be cleared or buffered. Dehydration may occur alongside this condition, but it is seldom the only explanation when the gap is clearly elevated.
Common causes include excess lactic acid, ketoacidosis, and toxins. Lactic acidosis can happen when tissues do not get enough oxygen or blood flow, which may occur in severe illness or substantial volume depletion. Ketoacidosis can occur with diabetes, prolonged fasting, alcohol use, or very low carbohydrate intake. Certain toxins and medications can also produce a harmful acid load.
These causes matter because they are actual metabolic problems, not just concentration effects from dehydration. A person may be dehydrated and also have one of these conditions. In that case, the dehydration may worsen the issue, but the main concern is the root acid accumulation.
If the anion gap is high, the rest of the panel becomes important. Low blood bicarbonate, a changing chloride pattern, and other signs of electrolyte disturbance can support the diagnosis. The best approach is not to focus on one number alone, but to ask whether the pattern fits a known cause of metabolic acidosis.
Decreased Anion Gap: Other Possible Causes
A reduced anion gap is less common than a elevated one, and dehydration is generally not the primary reason. A leading explanation is hypoalbuminemia, since albumin is a key negatively charged protein. If effect of albumin on AG albumin is low, the calculated gap can drop even if there is no major acid-base disorder.
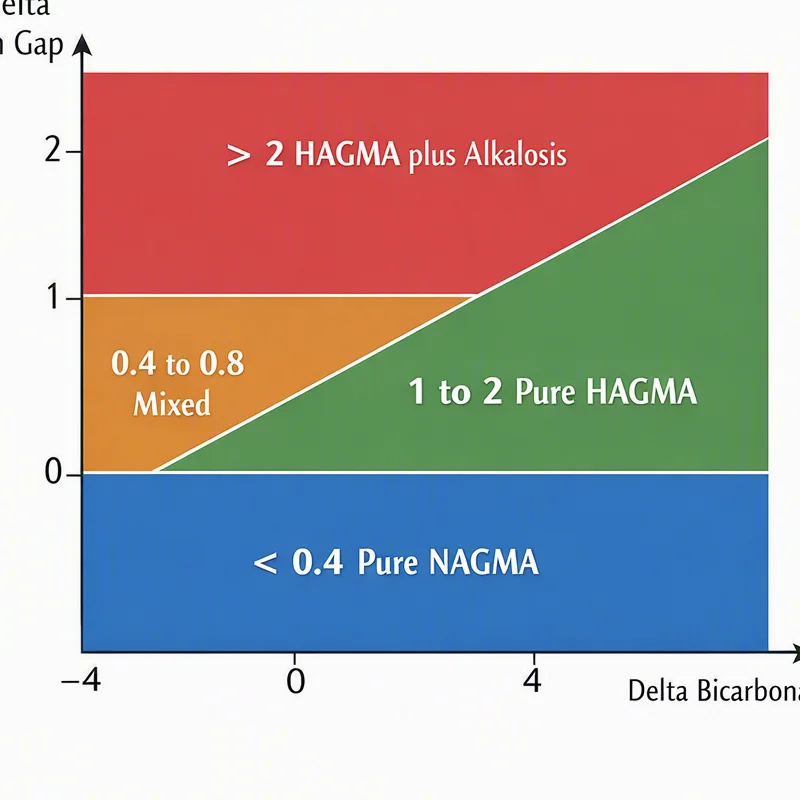
Another possible cause is multiple myeloma or other conditions that elevate abnormal proteins in the blood. These proteins may behave as positive ions or otherwise alter the balance between measured and unmeasured particles. In such cases, the low gap can be a clue that more testing is needed.
Lab error is also a real possibility. Because the anion gap is calculated from several measured values, a small mistake in one input can create a misleading result. Repeating the electrolyte panel or reviewing the sample handling may help if the number does not fit the clinical picture.
When a low result appears, clinicians often review the entire basic metabolic panel, the albumin level, and any signs of protein disorders or medication effects. As with a high result, the goal is to identify the actual cause rather than assuming the calculator result is the diagnosis.
Symptoms Requiring Medical Attention
Some symptoms suggest that a changed anion gap may be part of a more significant illness. Confusion, rapid breathing, and vomiting can occur when the body is dealing with acid-base problems or severe dehydration. Such symptoms need prompt attention, especially if they come on quickly or worsen.
Severe dehydration can lead to dizziness, weakness, dry mouth, very dark urine, fainting, and reduced urine output. If severe dehydration is paired with abnormal blood chemistry, the risk of kidney strain and metabolic complications increases. That is why symptom evaluation is equally important as the number itself.
Emergency or urgent care may be needed when symptoms suggest worsening acid-base imbalance, poor circulation, or inability to keep fluids down. A clinician may order repeat medical testing to check the anion gap, serum bicarbonate, kidney markers, and other data points. Symptoms together with lab results guides the next step.
If you are using an anion gap calculator and the number is abnormal, do not rely on the calculator alone if you feel unwell. Symptoms can reveal a problem that the number only hints at. In that situation, timely medical evaluation is the safest choice.
Common Questions About Dehydration and the Anion Gap
Can dehydration cause a high anion gap?
Dehydration can be associated with a high anion gap, but usually indirectly. Fluid loss can reduce blood volume, cause hemoconcentration, and contribute to kidney stress or poor tissue perfusion. Those changes may raise the gap if they lead to metabolic acidosis, lactic acidosis, or ketone buildup. Dehydration alone is not usually the full explanation.
Can dehydration cause a low anion gap?
Dehydration is not a common cause of a low anion gap. Low results are more often linked to hypoalbuminemia, multiple myeloma, lab error, or other shifts involving positive ions. If dehydration is present, it may affect lab values, but a low gap usually calls for a broader review.
What’s the normal anion gap range?
The anion gap range is influenced by the lab, the instrument, and whether albumin is considered. Most labs use a tight expected range, but there is no single fixed value. For best results interpretation, check your result with the range printed on the report and interpret it in the context of the electrolyte test panel and serum bicarbonate.
Should I drink water before repeating an electrolyte test?
If dehydration may have affected the result, moderate water intake may help normalize fluid balance balance, but do not assume hydration alone will explain the abnormality. A repeat electrolyte test panel or BMP should be done according to the instructions from your clinician. If you have vomiting, confusion, or trouble keeping fluids down, seek clinical evaluation rather than trying to self-correct the numbers.
When should a changed anion gap be evaluated by a doctor?
A changed result should be evaluated when it is clearly outside the expected normal range, when it comes with symptoms like confusion, increased breathing rate, or nausea and vomiting, or when there are signs of significant dehydration or kidney dysfunction. A clinician may review blood urea nitrogen, serum creatinine, serum albumin, and the full blood chemistry to identify the possible cause and decide whether more testing is needed.