How the anion gap Assesses
The anion gap is a computed value from a basic electrolyte panel that helps assess blood test interpretation in suspected acid-base problems. It reflects the relationship between major measured ions, especially serum sodium, serum chloride, and serum bicarbonate. In plain language, the anion gap estimates the amount of unmeasured ions in the blood and can serve as a practical diagnostic marker for certain biochemical problems.
Because the body works to maintain electroneutrality, the overall positive and negative charges in blood should stay balanced. When measured ions shift, the anion difference can point toward an underlying acid-base disorder. A change in the gap often indicates a metabolic derangement such as metabolic acidosis, where acids increase or bicarbonate is reduced.
The concept is especially helpful in serum chemistry because it gives clinicians a quick clue about whether the patient may have a high anion gap, a normal anion gap, or a low anion gap. That clue can reduce the list of possible causes and support further testing.
How an Anion Gap Calculator Works
An anion gap calculator relies on a basic calculation formula using common laboratory values. Many calculators prompt for serum sodium, serum chloride, and serum bicarbonate. Some calculators also allow potassium, which produces a potassium value-based adjustment to the result.
The calculator runs an adjusted calculation that reflects the underlying chemistry of the blood. Sodium is the main measured cation, while chloride and bicarbonate are major measured anions. The remaining difference helps estimate unmeasured ions. This can be valuable in blood test interpretation because the result may suggest a hidden acid load, a change in bicarbonate level, or an abnormal variation in the sodium chloride balance.
In practice, the calculator is a fast method for understanding whether there is a gap in the measured ions that could indicate a specific problem. It does not replace a full clinical review, but it can be a helpful first step in assessing acid-base balance.
Anion Gap Formula Using and Omitting Potassium
There exist two common approaches to compute the gap: a classic formula and a potassium-inclusive formula. This traditional method usually uses sodium, chloride, and bicarbonate. The potassium-based version adds serum potassium to the cation side of the equation.
One common traditional formula is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
The potassium-inclusive formula is:
Anion gap = (serum sodium + serum potassium) - (serum chloride + serum bicarbonate)
Both methods can be valid, but they do not produce the same number. The potassium-inclusive formula usually gives a slightly higher value because potassium is added to the cation total. As a result, the normal range depends on which formula is used and on the laboratory reference range reported by the lab.
Many clinicians focus on whether the result falls within the expected reference interval for that specific method. A calculator should clearly identify whether it is using the traditional or potassium-inclusive approach, since misreading the formula can lead to confusion in clinical interpretation.
How to Input Blood Test Values Correctly
Reliable results are based on entering the correct numbers for blood sodium, chloride, bicarbonate, and when applicable blood potassium. The numbers should come from the same specimen and same time period whenever possible, since mixed timing can distort the result.
Below are the key points to check:
- Enter the reported serum sodium value exactly as listed. Input serum chloride from the same panel, not a guessed value. Select the measured serum bicarbonate or total CO2 if that is what the lab provides. If the calculator includes blood potassium, use the serum potassium value from the same blood sample. Review units carefully so the inputs fit the calculator’s expected format.
Minor input errors can create a misleading low gap result or hide a true high anion gap. If the numbers seem inconsistent with the patient’s condition, confirm the laboratory values before drawing conclusions.
Reading a Elevated Anion Gap
A high anion gap often suggests additional acids are present in the circulation. This is a common pattern in metabolic acidosis and is frequently called increased gap acidosis. The key causes include lactic acidosis, ketoacidosis, kidney failure, and toxic alcohol exposure or other toxic intake.
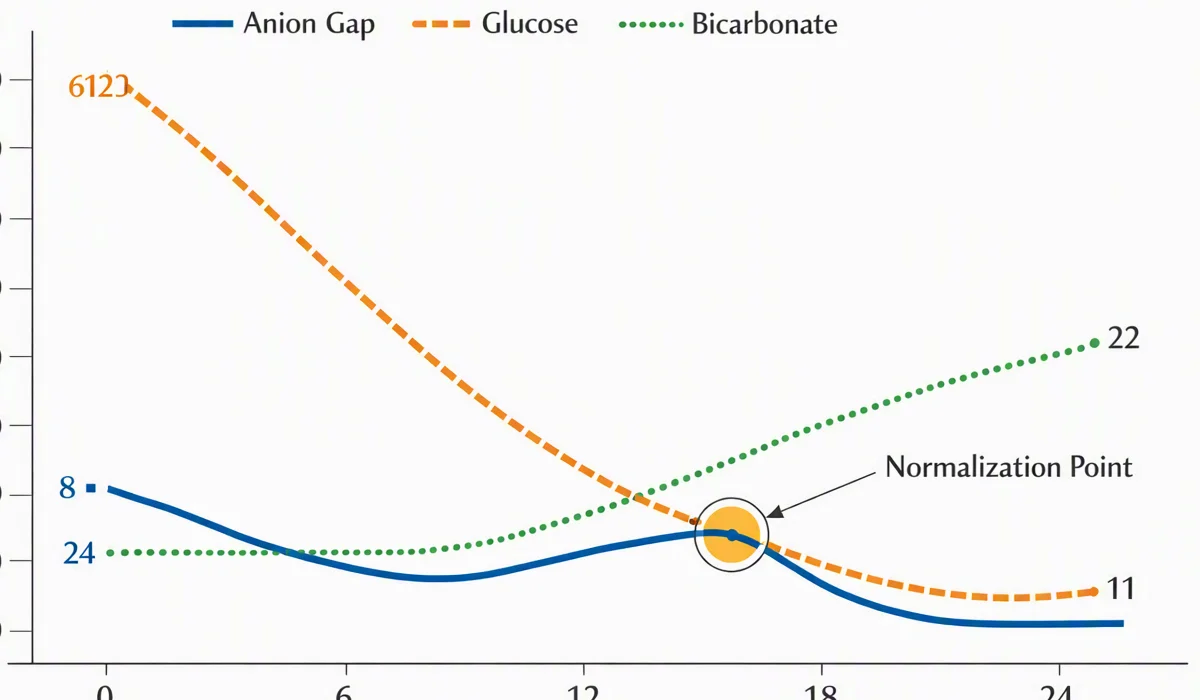
In lactic acid buildup, lactate rises because of poor oxygen delivery, shock, severe infection, or impaired metabolism. In ketoacidosis, ketones increase due to insulin deficiency, starvation, or alcohol-related metabolic states. Kidney failure can reduce acid excretion and allow unmeasured acids to build up. Toxic alcohols such as methanol or ethylene glycol can also produce a significant gap because their metabolites are acidic.
When the gap is high, the central question is not only what the number is, but what it means in the broader clinical setting. Symptoms, medication history, kidney function, glucose, lactate, ketones, and toxicology may all matter. The anion gap is a clue, not the final diagnosis.
Reading a Typical or Decreased Anion Gap
A anion gap in the normal range does not rule out acid-base disease. It may simply mean the body’s tested electrolytes are in equilibrium within the expected range. Certain types of metabolic acidosis, notably with a rise in chloride, may appear as a normal gap rather than a high one.
A reduced anion gap is uncommon and requires careful review. One major cause is hypoalbuminemia, because albumin is a negatively charged protein that makes up part of the unmeasured anion pool. When albumin is low, the gap can drop even if there is no major acid-base problem.
Other explanations include lab error, hyperchloremia, and paraproteinemia. Hyperchloremia can lower the gap because chloride rises relative to sodium and bicarbonate. Paraproteinemia, such as that seen in some plasma cell disorders, may also distort the expected balance of ions. Because of this, a low value should be compared against the full serum chemistry panel and repeated if needed.
In many cases, the anion gap clinical significance most useful next step is to look for a measurement issue, verify albumin, and evaluate whether the result aligns with the patient’s condition. A low gap can be real, but it can also be a clue that the sample or calculation should be reviewed.
When Potassium Changes the Result
Including serum potassium in the formula can alter the final number, but the size of the change is often limited. The reason some calculators use a potassium-inclusive formula is tied to electroneutrality: potassium is a true cation and adds to the total positive charge in the blood.
In routine practice, potassium may slightly raise the calculated gap, yet the clinical significance depends on how the result is being used. If the potassium value is normal, the difference between the standard and potassium-inclusive methods may not affect management. If potassium is markedly abnormal, the adjusted anion gap can provide a more complete picture of the electrolyte state.
That said, most clinicians still rely on the traditional approach because it is widely used in labs and textbooks. The potassium-inclusive method can be especially useful when a calculator is designed to reflect the full measured cation load and when you want a more detailed view of the patient’s electrolytes.
The practical point is this: potassium matters, but whether it affects the interpretation depends on the scenario. A calculator that accepts potassium can be a better choice for detailed review, while still requiring sound clinical interpretation.
Limitations of Internet Anion Gap Calculators
Online calculators are useful, but they have important drawbacks. To begin with, they use fixed reference limits that may not match every lab’s lab reference range. Different analyzers, populations, and formulas can produce different expected values. A number that looks abnormal in one setting may be acceptable in another.
Next, many calculators do not adjust for albumin correction. Because low albumin https://anion-gap-help263.theglensecret.com/anion-gap-calculator-for-chloride-shift-interpretation can lower the anion gap, uncorrected results may underestimate the presence of an acid load. A proper review may require considering albumin as well as the measured electrolytes.
Also, blood gas and chemistry results are not interchangeable. A venous blood gas may help assess pH and bicarbonate, but its values are not identical to a standard chemistry panel. That difference matters when evaluating metabolic acidosis or a suspected acid-base disorder.
Finally, calculators cannot replace clinical context. A result must be interpreted alongside symptoms, medications, kidney function, glucose, ketones, lactate, and other lab findings. The calculator is a tool for pattern recognition, not a standalone diagnosis.
FAQ
What is an anion gap calculator used for?
An anion gap calculator is used for blood test interpretation when reviewing a serum chemistry panel. It helps estimate whether there is a hidden acid load, making it useful for detecting metabolic acidosis, especially high anion gap states. It can also help identify a normal anion gap or low anion gap that may need further review.
Should potassium be included in the anion gap formula?
Potassium is included in some formulas, especially the potassium-inclusive formula, but not all calculators use it. The traditional formula is more common, while the potassium version may better reflect total measured cations in certain cases. Whether to include potassium depends on the calculator design, lab method, and the purpose of the clinical interpretation.
What’s a normal anion gap range?
The typical range depends on the calculation method and the lab. Some labs use a separate reference range for the traditional formula than for the potassium-based method. Because of this, the preferred approach is to compare the result with the specific reference range reported by the laboratory rather than relying on one universal number.
What may a high anion gap mean?
A high anion gap usually indicates metabolic acidosis from unmeasured acids. Common causes include lactate buildup, ketone-related acidosis, renal impairment, and poisonous alcohols or other forms of toxic ingestion. It is a clue that should be assessed with the rest of the electrolyte panel and the patient’s clinical context.
Can lab error or low albumin cause a low anion gap?
Yes. A low anion gap can result from laboratory error or from hypoalbuminemia, since the albumin level is a major unmeasured anion. Other causes include hyperchloremia and monoclonal protein excess. If the result is unexpected, it is reasonable to confirm the blood sodium, blood potassium, chloride level, and serum bicarbonate values and examine the full laboratory picture.