What Is the Anion Gap?
The gap calculation is a computed result used to aid in assessing serum electrolytes and assess acid-base status. It compares the main measured positively charged ions, especially Na, with the measured negative ions, mainly chloride and bicarbonate. This basic lab calculation can reveal whether there are excess acids or other undetected anions affecting the body’s internal chemistry.
Clinically, the anion gap is a valuable diagnostic tool for identifying an underlying metabolic problem. It is often reviewed as part of a more comprehensive electrolyte test panel or blood chemistry assessment. Although the value is not a diagnosis by itself, it can point toward an acid-base imbalance that deserves further investigation.
The basic idea is clear: if the difference between the measured cations and anions is larger than expected, the extra gap often reflects acids that are not directly measured on routine labs. That is why the anion gap plays a key role in reading the anion gap and in evaluating acidosis.
Why Albumin Alters the Anion Gap
Albumin is as one of the most significant unmeasured anions in the blood. Since albumin carries a negative charge, it plays a role significantly to the usual gap seen on chemistry testing. When serum albumin is low, the anion gap may appear falsely low even if important acids are present.
This is where hypoalbuminemia becomes clinically important. In people with low albumin, the measured anion gap can minimize the severity of an acid-base problem. A patient may have significant retained acids, but the lab value can look deceptively normal because the negative charge from albumin has been reduced.
This occurs is related to protein charge. Albumin normally helps balance the electrical environment in plasma. If albumin drops, the body compensates in ways that can shift chloride and other ions, changing the appearance of the gap. This is why clinicians often use an albumin correction or an albumin-adjusted anion gap to improve diagnostic accuracy.
Using the correction helps with clinical utility because it makes the result more informative when evaluating a possible electrolyte imbalance or compensated acidosis. Put simply, low albumin can hide the true acid burden, and correcting for it gives a clearer picture of the patient’s acid-base disorder.
Anion Gap Formula and Albumin Correction
The typical anion gap formula is:
Anion gap = Sodium - (Chloride + Bicarbonate)
Some laboratories may use slight variations, but this is the standard structure for a routine lab calculation. The result is then checked against a lab’s reference range to determine whether it is below normal, normal, or high.
To account for reduced albumin, clinicians use an albumin correction formula. A commonly used approach is to add about 2.5 mEq/L to the calculated gap for every 1 g/dL decrease in albumin below 4.0 g/dL. This creates a corrected anion gap that more clearly shows the patient’s actual acid burden.
Corrected anion gap = Measured anion gap + 2.5 × (4.0 - serum albumin in g/dL)
This correction factor is especially helpful in patients with low albumin, because the uncorrected value may seem closer to a normal anion gap even when extra acids are present. The goal is not to replace clinical judgment, but to support interpretation.
With this adjustment, a hidden high anion gap metabolic acidosis may become easier to recognize. The corrected value can also help differentiate true abnormal acid accumulation from a value that only appears normal because albumin is reduced.
How to Use the Anion Gap Calculator
An anion gap calculator streamlines the process by combining the key lab values into one result. To operate it, enter the available values from the electrolyte panel:
- Serum sodium Blood chloride Serum bicarbonate Blood albumin
The calculator first applies the standard lab calculation for the anion gap. Then it adds albumin correction to produce the corrected anion gap. This makes it easier to calculate anion gap values quickly while also accounting for serum albumin abnormalities.
In practical use, the calculator supports more efficient interpretation of serum electrolytes and helps clinicians decide whether the pattern fits a metabolic acidosis. It is especially useful in cases where the acid-base picture is complex, the patient has significant illness, or the laboratory data indicate mixed disorders.
For example, a patient with low bicarbonate and low albumin may still have a larger acid burden than the raw anion gap suggests. By using the calculator, the clinician can better assess acid-base status and determine whether the problem is more consistent with elevated unmeasured acids.
Reading High versus Normal Anion Gap Results
A increased anion gap metabolic acidosis often suggests that more acids are circulating in the bloodstream. These acids increase the gap because they are not directly measured on routine chemistry testing. Common causes include elevated lactate, ketone-driven acidosis, renal impairment, and toxic ingestions.
In contrast, a non-anion gap metabolic acidosis is typically associated with bicarbonate depletion or failure to excrete acid without a marked rise in unmeasured acids. Because the uncorrected value may seem normal in the setting of low albumin, albumin adjustment is important before concluding that the acid-base picture is truly normal.
Lactic acidosis occurs when anion gap reference by lab lactate accumulates, often due to tissue hypoperfusion, severe illness, or impaired metabolism. Ketone-related acidosis occurs when ketone bodies rise, such as in diabetes, starvation, or alcohol-related states. Both produce a true elevation in the gap and require prompt evaluation.
Context is essential when interpreting the result. A corrected value that changes from normal to elevated may alter the entire diagnostic approach. That is the value of anion gap assessment: it helps clinicians identify whether the acid-base pattern is likely due to excess acids, bicarbonate loss, or a mixed disorder.
Typical Causes of Abnormal Anion Gap
Several conditions can increase the anion gap. One major cause is renal failure, which limits the body’s ability to eliminate acid. As kidney function worsens, acids build up and the gap may rise. Related to this is uremia, where retained waste products and acid retention cause the abnormal value.
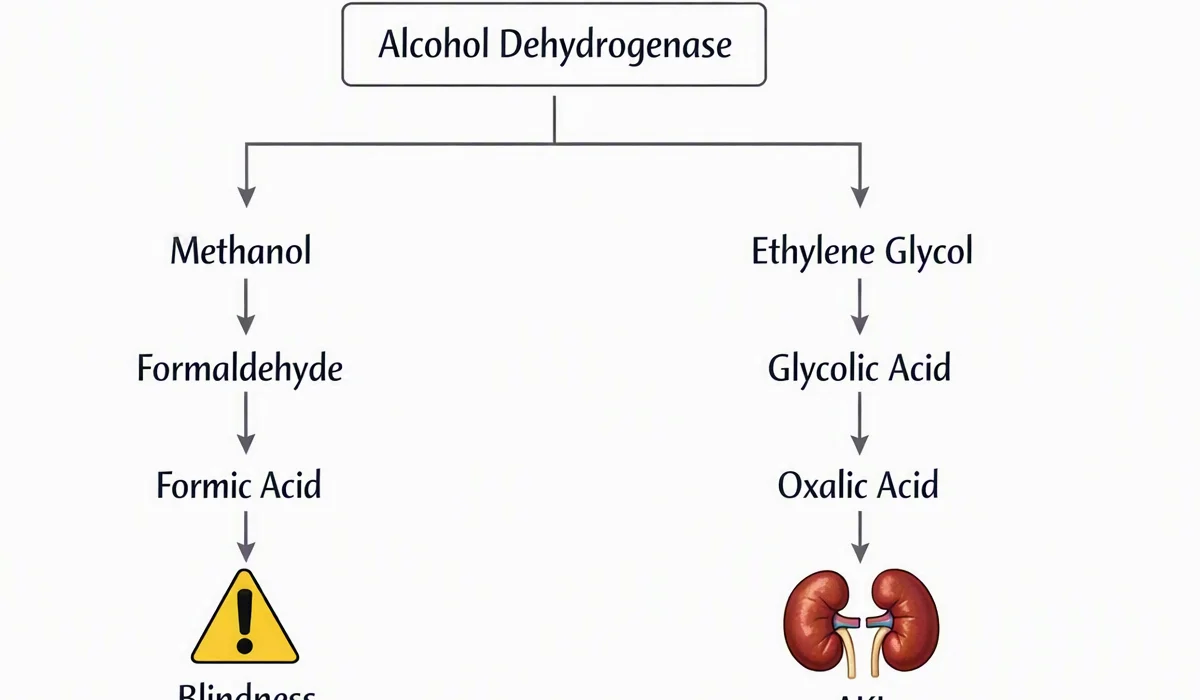
Another important category is toxic alcohols, including substances that create acid metabolites after ingestion. These can generate dangerous high-gap acidosis and require immediate recognition. The presence of a high gap in the right clinical setting may help narrow the differential diagnosis promptly.
Lactate is also a major contributor. Elevated lactate may result from shock, infection, hypoxia, seizures, or other conditions that drive anaerobic metabolism. Since lactate is an unmeasured anion on standard panels, it can widen the measured gap markedly.
Further causes of abnormal values include ketone accumulation, medication effects, and other forms of retained acids. The final interpretation should always relate the lab pattern to the clinical presentation. In other words, the anion gap is a method for reasoning through the source of the metabolic acidosis, not a stand-alone answer.
Limitations and Practice Considerations
Although the anion gap is valuable, it has significant limitations. A result can be altered by measurement error in the corresponding electrolyte panel, especially if sodium, chloride, or bicarbonate values are off. Small lab differences can alter the final calculation more than clinicians expect.
Reading the result also relies on the lab’s reference range. Different laboratories use different methods and calibration standards, so the “normal” value may fluctuate. A result that looks abnormal in one setting may fall within the expected range in another.
The anion gap should also be interpreted alongside additional data, including the arterial blood gas when available. The blood gas helps clarify pH, respiratory compensation, and whether the patient has a mixed acid-base state. When paired with the chemistry panel, it gives a clearer view of the patient’s acid-base status.
In the end, a corrected value strengthens interpretation but does not replace bedside assessment. Clinical context, medications, kidney function, perfusion, and symptoms all count. The best use of the calculator is as a diagnostic aid that supplements, rather than takes the place of, medical reasoning.
Frequently Asked Questions
What is an anion gap calculator with albumin correction?
An anion gap calculator with albumin correction is a calculator that determines the standard anion gap and then modifies it for serum albumin levels. This assists produce a more accurate corrected anion gap, especially when albumin is low and the uncorrected value may underestimate the true acid burden. It is commonly used as a diagnostic aid in evaluating metabolic acidosis.
Why do you correct the anion gap for albumin?
You correct the anion gap for albumin because albumin is a major unmeasured anions contributor in blood. In hypoalbuminemia, the raw anion gap can appear lower than expected, which may hide a significant acid-base problem. Albumin correction improves clinical interpretation and helps reveal true anion gap interpretation more accurately.
How do you calculate the corrected anion gap?
First, use the anion gap formula: sodium minus the sum of chloride and bicarbonate. Then apply the albumin correction formula by adding about 2.5 mEq/L for each 1 g/dL that serum albumin is below 4.0 g/dL. This gives the corrected anion gap and helps account for low albumin when you interpret the result.
What does a high anion gap mean?
A high anion gap usually suggests high anion gap metabolic acidosis, which means there are extra acids in the blood that are not directly measured on routine labs. Common causes include lactic acidosis, ketoacidosis, renal failure, uremia, and toxic alcohols. The result should be interpreted with the electrolyte panel, symptoms, and other clinical data.
Can a regular anion gap also indicate metabolic acidosis?
Absolutely. A normal anion gap metabolic acidosis can still be present, especially if bicarbonate is decreased but the gap remains within the normal range. Also, hypoalbuminemia can lead a true high-gap acidosis appear normal unless you use corrected albumin value. That is why the corrected value and overall diagnostic value of the calculator are so important for accurate acidosis assessment.