What Is the Anion Gap?
The anion gap is a calculated value that helps clinicians gauge the difference between regularly checked electrolytes in the blood. It is most often used as a diagnostic clue in metabolic acidosis, where it can help identify whether extra acids or other unmeasured anions are present.
At its core, the anion gap shows the relationship between sodium, chloride, and bicarbonate. Because the body maintains electrical balance, the measured positive and negative charges should remain equal. When they do not, the gap can suggest an electrolyte imbalance or another metabolic abnormality that needs further assessment.
The anion gap is not a direct test. Instead, it is a calculated estimate that supports acid-base balance evaluation and broader acid-base disorders evaluations. In practice, it is best viewed as a initial and clinical interpretation tool rather than a independent diagnosis.
How the Anion Gap Calculator Works
An anion gap calculator applies a basic equation based on routine laboratory values. The usual method is:
Anion gap = Sodium − (Chloride + Bicarbonate)
Some calculators also include potassium, even though many clinicians leave it out because the value typically makes little difference in everyday interpretation. If potassium is included, the formula becomes:
Anion gap = Sodium + Potassium − (Chloride + Bicarbonate)
This process uses serum electrolytes from a serum chemistry panel or broader metabolic panel. The output can indicate whether there may be a rise of acidic substances or another shift in measured ions. Since bicarbonate is often reduced in acidosis, the calculator is especially valuable in the assessment of serum bicarbonate values and related acid-base interpretation.
The calculator is a useful diagnostic aid because it transforms everyday laboratory values into a more useful assessment of acid-base status. If used correctly, it supports clinical decision making by identifying patterns that deserve further attention.
Typical Anion Gap Versus Elevated Anion Gap Acidosis
Grasping the distinction between standard anion gap metabolic acidosis and increased anion gap metabolic acidosis is important for correct interpretation. These are forms of metabolic acidosis, but they result from different mechanisms.
In normal anion gap metabolic acidosis, the bicarbonate falls, but the loss is usually matched by a rise in chloride. This pattern is often called chloride-responsive acidosis. The anion gap persists within the expected range because the decrease in one measured ion is offset by an increase in another.
In increased anion gap metabolic acidosis, bicarbonate falls and there are additional unmeasured acids in the blood. These acids leave behind their anions, which widens the gap. This pattern suggests a greater accumulation of unmeasured anions and typically requires a search for causes such as lactic acidosis, ketoacidosis, renal dysfunction, or toxic exposures.
In practice, the distinction matters because it focuses the differential diagnosis. A normal anion gap pattern suggests toward causes of bicarbonate loss, while a elevated anion gap pattern points toward acid production, acid retention, or impaired clearance.
How to Interpret the Result
Evaluating an anion gap result takes more than comparing the number to a reference range. The first step is to determine whether albumin is low, because albumin is a major unmeasured anion and strongly influences the value. When albumin is reduced, the gap may look falsely normal even when clinically important acidosis is present.
At this point the corrected anion gap becomes important. The correction adjusts the measured result upward when albumin is low, improving diagnostic accuracy. This process is often called albumin adjustment or anion gap correction, and it can reveal hidden high-gap acidosis that would otherwise be missed.
The delta gap is another important concept. It compares the change in anion gap to the change in bicarbonate and can uncover mixed acid-base disorders. For example, a patient may have high anion gap acidosis plus a concurrent metabolic alkalosis, which can make the bicarbonate appear less reduced than expected.
Good interpretation always integrates the calculator result with the patient’s clinical assessment. Symptoms, history, medications, renal function, and other laboratory findings matter. A single number rarely gives the full picture.
Helpful interpretation questions include:
- Is the the anion gap truly elevated after albumin correction? Does the bicarbonate change follow the expected pattern? Are there signs of mixed acid-base disorders? Does the clinical context suggest lactate elevation, ketones, renal impairment, or toxins?
Typical Causes of Elevated Anion Gap
An elevated anion gap usually means that additional acids are present or that acid clearance is impaired. Common causes include lactic acidosis, ketoacidosis, renal failure, uremia, and specific toxins.
Lactic acidosis occurs when lactate accumulates, often due to tissue hypoperfusion, severe illness, seizures, or other situations of increased anaerobic metabolism. Since lactate is an unmeasured anion, the anion gap rises as bicarbonate falls.
Ketoacidosis can occur in diabetes, prolonged fasting, or alcohol-related metabolic states. Ketone bodies act as unmeasured acids, causing a high anion gap metabolic acidosis that often requires urgent treatment.
Renal failure and uremia limit the body’s ability to excrete acid and maintain normal acid-base homeostasis. As retained acids accumulate, the anion gap can rise markedly.
Toxins are another major group. Certain ingestions can cause profound acid-base disruption and may present with an increased gap. In these cases, the calculator is simply one part of the evaluation, not the entire diagnosis.
Other causes may also exist, but these major categories account for many clinically important cases of elevated anion gap metabolic acidosis. Spotting the pattern helps guide appropriate testing and faster treatment.
Medical Perspective and Caveats
The anion gap is helpful, but it has notable limitations. The result must always be interpreted alongside the blood gas, serum chemistry panel, and the overall clinical picture. It cannot substitute for bedside judgment or the full evaluation of acid-base disorders.
One limitation is inconsistency in the laboratory reference range from one lab to another. Different analyzers, different measurement methods, and different reporting or omission of potassium can all alter the value. That means a “normal” number in one setting may not map exactly to another setting.
Another limitation is the effect of albumin. Without correction, the anion gap may underestimate clinically meaningful abnormalities. Also, the gap does not determine the exact acid responsible; it only suggests that unmeasured anions may be present.
A blood gas helps confirm acid-base status by showing pH and carbon dioxide, while the serum chemistry panel supplies the electrolyte data needed for calculation. Together, these results strengthen more accurate diagnostic interpretation. The best use of the calculator is as part of a structured patient evaluation, not as a replacement for it.
Important pitfalls include:
- Believing a normal gap excludes all clinically significant acidosis Ignoring low albumin when evaluating the result Failing to compare the gap with bicarbonate using the delta gap Applying the calculator without considering the blood gas and clinical context
Step-by-Step Illustrative Calculations
An example calculation helps illustrate how the formula works in actual use. Look at these electrolyte values:
- Sodium: 140 Chloride: 102 Bicarbonate: 18
With the formula, the anion gap is:
140 − (102 + 18) = 20
This finding indicates a elevated anion gap metabolic acidosis, assuming the local reference range is lower than 20. The next step would be to review the clinical picture for causes such as lactic acidosis, ketoacidosis, renal failure, or toxins.
Now add albumin to the picture. If albumin is low, the measured gap may understate the problem. A corrected anion gap can be calculated using albumin adjustment to improve the estimate of the true burden of unmeasured anions.
For a second case, imagine a patient with https://anion-gap-tool758.yousher.com/can-working-out-increase-the-anion-gap the following values:
- Sodium: 138 Chloride: 112 Bicarbonate: 18
The calculation is:
138 − (112 + 18) = 8
This can suggest a normal anion gap metabolic acidosis pattern, especially if bicarbonate is low and chloride is relatively high. In that setting, the interpretation may point more toward bicarbonate loss rather than excess unmeasured acids.
In a more advanced case, the corrected bicarbonate and the delta gap can be used together. If the anion gap is elevated but bicarbonate is not as low as expected, a mixed disorder may be present. That kind of interpretation is especially valuable when acid-base balance is complex and multiple processes overlap.
These illustrations show why calculator use is only the first step. The final interpretation depends on whether the numbers match the clinical story and whether additional testing supports the same conclusion.
Frequently Asked Questions about the Anion Gap Calculator
What does a Anion Gap Calculator measure?
An Anion Gap Calculator calculates the difference between key measured electrolytes, usually sodium, chloride, and bicarbonate. The result estimates whether there are additional unmeasured anions in the blood and helps evaluate metabolic acidosis and other acid-base disorders.
What is a normal anion gap range?
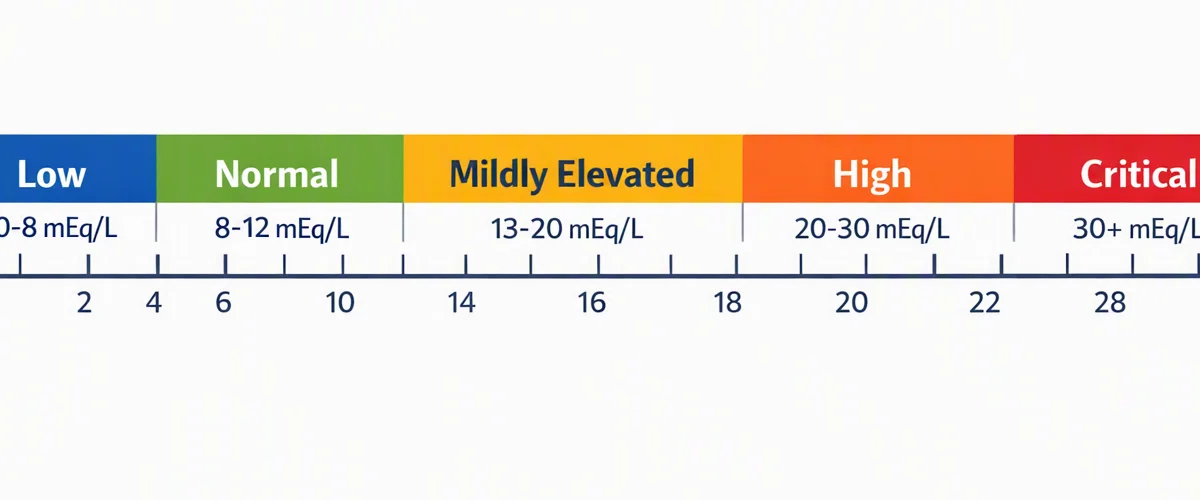
The normal anion gap range is based on the laboratory reference range used by the testing method. Because labs differ, it is best to understand the result using the reference range provided with the patient’s serum chemistry panel and the overall clinical context.
Why do you correct the anion gap for albumin?
You correct the anion gap for albumin because albumin is a major unmeasured anion. When albumin is low, the measured anion gap may appear falsely normal. Correcting for albumin improves diagnostic accuracy and helps reveal hidden metabolic acidosis.
Which conditions cause a high anion gap metabolic acidosis?
Common causes include lactic acidosis, ketoacidosis, renal failure, uremia, and toxins. These conditions elevate unmeasured anions or decrease acid clearance, which increases the anion gap and lowers bicarbonate.
How does the delta gap used in anion gap interpretation?
The delta gap compares the change in anion gap with the change in bicarbonate. It helps identify mixed acid-base disorders, such as high anion gap metabolic acidosis combined with metabolic alkalosis or a normal anion gap process. This keeps interpretation more precise during patient evaluation.