What the Anion Gap Measures
The anion gap is a useful clinical indicator that assists clinicians and patients understand lab results as part of a broader assessment of pH balance. An anion gap calculator estimates the variation between measured serum electrolytes in the blood chemistry panel, which reflects electrolyte balance and can point toward various acid-base disorders.

In simple terms, the anion gap compares the key positively charged and negatively charged ions reported on a routine electrolyte panel. The most important values are sodium, chloride, and bicarbonate. Because not all ions are directly measured, the anion gap can reveal whether there are extra unmeasured acids in the bloodstream.
This makes the anion gap especially important in metabolic acidosis evaluation. A high result can suggest extra acid accumulation, while a normal result may reflect a different pattern of acid loss or compensation. The calculation does not work alone, but it gives important context for clinical interpretation of the anion gap lab result.
Think of it as part of a larger serum electrolytes review. It is not a standalone diagnosis, but it can guide the next steps in patient assessment and help rule out causes of abnormal blood chemistry.
How to Determine the Anion Gap
The standard anion gap formula uses serum sodium, serum chloride, and serum bicarbonate. The usual version is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
This equation estimates the variation between measured cations and anions. If you use an anion gap calculator, you simply enter the laboratory values from the basic metabolic panel or another electrolyte panel, and the tool calculates the result immediately.
Here is a simple example of how to calculate anion gap from lab results:
- Serum sodium: 140 Serum chloride: 102 Serum bicarbonate: 24
Using the formula: 140 - (102 + 24) = 14. That value can fall within a normal reference range, depending on the lab.
Some clinicians also use different formulas that include potassium, but the sodium-based version is the most common for routine clinical interpretation. No matter the version, the goal is the same: to detect patterns that may suggest metabolic acidosis or other shifts in acid-base balance.
Normal Anion Gap Range and Reference Values
The normal range for anion gap is influenced by the laboratory’s procedure and report format. That is why the exact lab reference range should always be checked alongside the result. Different analyzers, assays, and calculation methods can create lab variability.
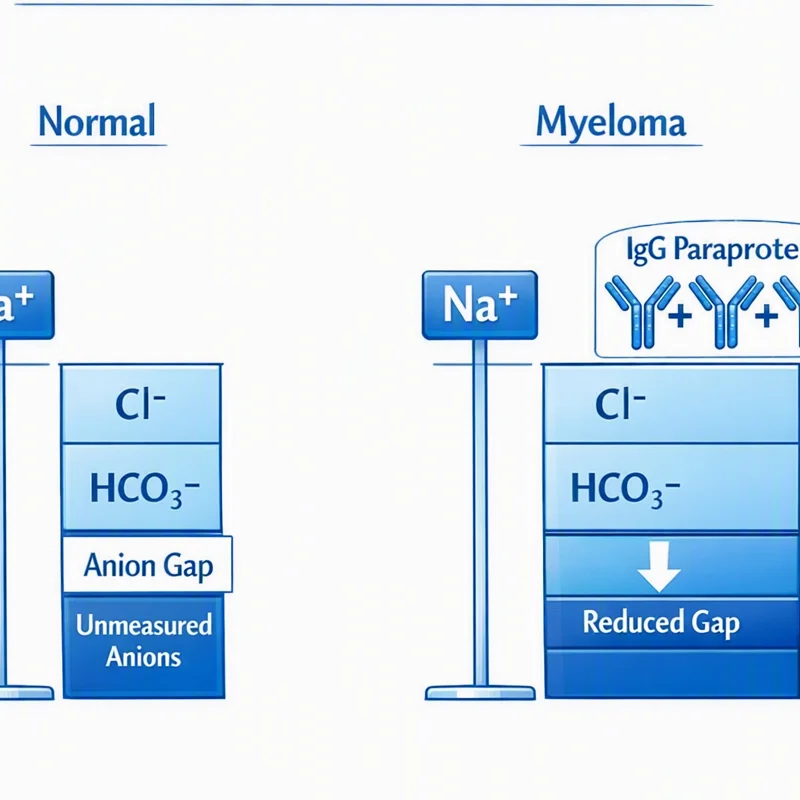
In many settings, the usual range is narrow, but the acceptable value may differ based on whether potassium is included and whether the result is corrected for albumin. Because of this, a result that looks “high” in one lab may be considered normal in another. Always use the specific lab reference values tied to that report.
Albumin also matters because it is one of the major unmeasured anions in blood. When serum albumin is low, the measured anion gap can appear falsely within range or low, even when an acid-base problem exists. That is why interpreting the number without considering albumin can lead to overlooked results.
In short, the “normal” value is not just a fixed number. It is a context-based result that must be interpreted with the lab’s stated reference range, the patient’s overall status, and other laboratory findings.
Adjusted Anion Gap and Albumin Correction
Low albumin is one of the most important reasons to modify the anion gap. Since albumin contributes significantly to the unmeasured anions in blood, a low albumin level can decrease the apparent gap. This is where albumin correction becomes helpful.
The corrected anion gap helps compensate for reduced serum albumin. This adjustment improves the accuracy of the result when evaluating possible acidotic states. If the gap is not adjusted, a clinically important elevation may be underestimated.
A common approach is to use a correction factor when albumin is below normal. While formulas may vary slightly by institution, the goal is the same: approximate what the anion gap would be if albumin were normal. This makes the result more accurate for clinical evaluation and clinical interpretation.
For example, a patient with low albumin may have an anion gap that appears normal, but after albumin compensation, the value may suggest hidden occult high anion gap acidosis. In real-world practice, this is why albumin should be reviewed whenever the anion gap is used to interpret lab results.
When using an Anion Gap Calculator, look for a version that includes albumin adjustment or allows you to manually apply the correction. This is especially helpful in complex cases and in patients with chronic illness, malnutrition, or inflammation.
Elevated Anion Gap Compared with Expected Anion Gap Acidosis
A major use of the anion gap is distinguishing high anion gap from expected anion gap acid-base acidosis. Each are patterns of metabolic acidosis, but they indicate different mechanisms.
In increased anion gap acidosis, unmeasured acids accumulate in the blood. Typical causes include lactic acidosis, ketone acidosis, and kidney failure. These conditions raise acid production or impair acid clearance, which increases the gap.
In typical anion gap acidosis, the bicarbonate level decreases but the gap remains within the expected range because chloride goes up to maintain electrical balance. This pattern is often called chloride-rich acidosis. It is a distinct acid-base pattern from classic high gap states.
Recognizing the difference helps direct the next steps in metabolic acidosis evaluation. A high gap suggests evaluating for acid accumulation or toxin exposure. A normal gap suggests considering bicarbonate loss, renal tubular issues, or other causes of acid-base imbalance.
The anion gap therefore works as a clinical marker that narrows the differential. It does not replace the full assessment, but it helps connect the numbers to the likely physiology.

Common Causes of Altered Anion Gap Results
Abnormal anion gap results can indicate many conditions, and the most useful approach is to consider the patient context along with the laboratory findings. Typical causes of a high anion gap include lactic acidosis, ketoacidosis, renal failure, and uremia.
Lactate builds up when tissues are under stress and oxygen delivery or utilization is impaired. This can happen in severe illness, shock states, or other conditions that increase anaerobic metabolism. Elevated lactate is a frequent cause of high gap acidosis.
Ketoacidosis occurs when ketone production increases, often in diabetes, prolonged fasting, or alcohol-related metabolic states. It can create a significant anion gap increase and should be considered when https://anion-gap-test673.publishlane.com/posts/can-the-anion-gap-be-used-to-monitor-treatment blood glucose or ketones are abnormal.
Renal failure can reduce the kidneys’ ability to clear acids, leading to uremia and retention of unmeasured anions. This is another common cause of high gap abnormalities.
Other causes involve toxins and drug exposures. Salicylates can produce mixed acid-base findings and may elevate the gap. Other toxins can also contribute to an abnormal result, so history and medication review are key parts of the workup.
Because several conditions can overlap, the anion gap should be interpreted alongside symptoms, medication use, and the broader pattern of laboratory data.
How to Interpret Results Alongside Other Lab Tests
The anion gap becomes far more useful when interpreted with other tests. A basic metabolic panel supplies the core electrolyte values, but additional studies often explain the cause of the abnormality and direct treatment decisions.
An arterial blood gas can show pH, partial pressure of carbon dioxide, and bicarbonate in more detail, helping define the type and severity of the acid-base disorder. A venous blood gas can also be helpful in many settings, especially when repeated monitoring is needed and arterial sampling is not necessary.
The osmolar gap is another key companion test when toxins or unusual ingestions are possible. A high osmolar gap may suggest certain toxic alcohol exposures, while the anion gap may show concurrent metabolic changes.
When used together, these tests provide a structured clinical interpretation of acid-base balance. The anion gap helps identify unmeasured acids, the blood gas shows the physiologic effect, and the osmolar gap can point toward specific toxic causes. This combination improves the ability to rule out causes and determine whether the problem is a primary metabolic issue, a mixed disorder, or a compensatory response.
In real practice, the best results come from combining the anion gap formula with the rest of the lab picture rather than assessing one number in isolation.
When to Seek Medical Review
Certain anion gap findings need prompt review, especially when the result is paired with concerning symptoms or other abnormal labs. A very high or unexpected value may represent a time-sensitive problem that needs immediate attention.
Critical values should always be handled according to local lab policy and the patient’s condition. Even if the number is not formally flagged, a significant change from prior results can matter. Trend interpretation is often more useful than a single isolated number.
Seek urgent assessment when the abnormal result occurs with symptoms such as severe weakness, confusion, rapid breathing, vomiting, chest discomfort, or reduced consciousness. These findings may point to significant metabolic acidosis, toxic exposure, severe lactic acidosis, or another acute problem.
It is also important to use clinical judgment. The same anion gap value can mean different things in different patients depending on the reference range, albumin level, kidney function, and other laboratory findings. A number that seems mild in one case may be clinically important in another.
An anion gap calculator helps with decision-making, but it does not replace medical review. If the result is abnormal and the person is unwell, immediate evaluation is appropriate.
Anion Gap Calculator FAQ
What is an anion gap calculator used for?
An anion gap calculator is used to calculate anion gap values from lab results and support interpretation of lab results in the setting of acid-base balance. It is especially helpful in metabolic acidosis evaluation, where it can suggest whether the problem is likely to be a high anion gap state or a normal anion gap pattern. It also supports review of the anion gap lab result alongside the rest of the electrolyte panel.
How do you calculate the anion gap from lab results?
Use the anion gap formula: serum sodium minus the sum of serum chloride and serum bicarbonate. In other words, anion gap = serum sodium - (serum chloride + serum bicarbonate). It uses values from the basic metabolic panel or another electrolyte panel and is the usual way to calculate the result.
What is the normal anion gap range?
The normal range depends on the laboratory’s approach and reported lab reference range. Owing to lab variability, always check the result with the specific report rather than relying on a single universal number. Albumin and whether the value is corrected for albumin can also affect interpretation, so the best answer always comes from the exact laboratory context.
Why do you correct the anion gap for albumin?
You adjust the anion gap for albumin because hypoalbuminemia can make the gap look artificially low or normal. Since serum albumin contributes to unmeasured anions, albumin correction improves accuracy and may uncover hidden acid accumulation. A corrected anion gap is especially useful when trying to detect occult high gap acidosis.
What does a high anion gap mean?
A high anion gap usually means there are extra unmeasured acids in the blood, which often points to metabolic acidosis. Common causes include lactic acidosis, ketoacidosis, renal failure, and uremia. It can also be associated with salicylates or other toxins. The result should be interpreted together with symptoms, blood gas testing, and the rest of the laboratory findings for accurate clinical interpretation.