How the Anion Gap Measures in Acute Care
The anion gap is a fast, useful way to evaluate acid-base balance using routine electrolytes from the serum chemistry panel. In critical care, it helps recognize an underlying metabolic acidosis and aids early cause identification when a patient is deteriorating, ventilated, septic, or otherwise physiologically stressed.
An anion gap calculator is valuable because it turns a standard lab pattern into bedside action. Rather than looking at sodium, chloride, and bicarbonate as isolated values, the clinician can read them together as a marker of an acidotic state, anion deficit, or broader metabolic derangement. That makes the result valuable for diagnostic support and risk stratification.
Physiologically, the anion gap shows the difference between measured cations and measured anions in the bloodstream. Unmeasured anions such as lactate, ketones, and certain toxins can accumulate, altering acid-base balance. In contrast, changes in chloride can obscure a problem and produce a normal anion gap even when acidosis is present. Because of that, clinical interpretation must always consider the full laboratory result and the bedside context.
For critical care, the anion gap is not a stand-alone diagnosis. It is a screening clue that often suggests lactic acidosis, ketoacidosis, renal failure, or toxic ingestion. It can also help differentiate a primary acid-base disorder from a compensatory response. Used well, it becomes part of a systematic approach to acid-base disorder recognition.
Using an Anion Gap Calculator
An anion gap calculator relies on a basic anion gap formula using routinely ordered serum values. The classic calculation is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
Certain laboratories or clinicians use alternative formulas that include potassium, but the sodium-based version is the standard for bedside assessment. The important part is to apply the same method consistently and interpret the laboratory result in the context of the reference interval used by that lab.
Because the calculation is built from sodium, chloride, and bicarbonate, it is often available whenever an electrolyte panel is ordered. This creates an efficient tool for rapid clinical interpretation in critical care, especially when a patient is deteriorating and immediate trend monitoring matters.
Sequential Calculation Inputs
To use the calculator correctly, enter the following values from the patient’s serum chemistry:
- Serum sodium: the recorded sodium concentration Serum chloride: the recorded chloride concentration Serum bicarbonate: the measured bicarbonate concentration or total CO2, depending on the lab
Once these are entered, the calculator determines the anion gap automatically. In use, this is a quick bedside workflow: review the electrolyte panel, confirm units, and calculate the gap before moving to broader diagnostic support. If the patient has severe illness, the number should be interpreted alongside other signs of perfusion, ventilation, and organ function.
One important nuance is that serum bicarbonate may be altered by respiratory compensation or prior treatment. Therefore, the number should not be interpreted in isolation. It reflects the current serum chemistry pattern, but the broader acid-base disorder may be more complex.
Reading the Result at the Bedside
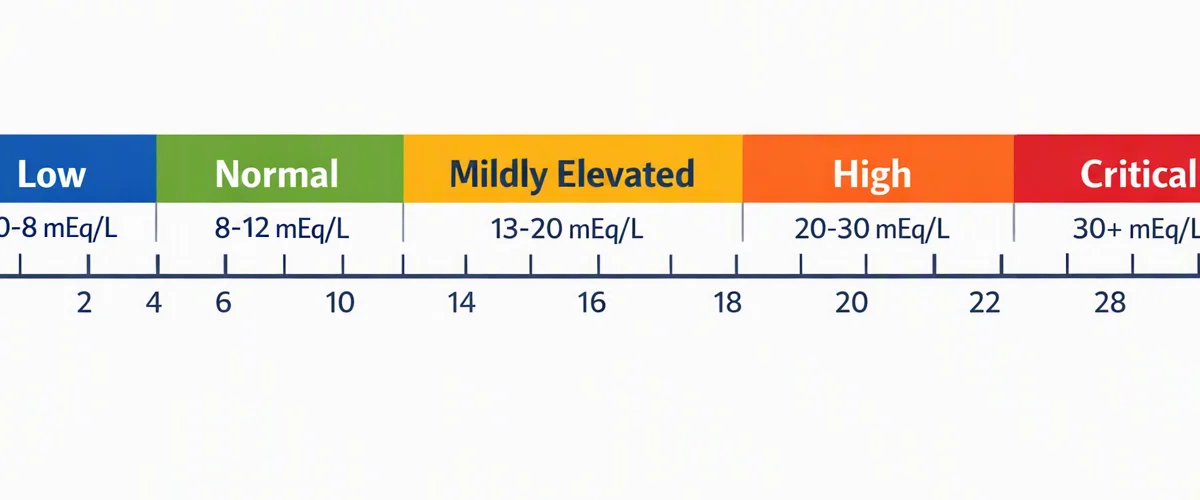
Interpreting the result begins with the normal range used by the laboratory. Although the exact reference interval can vary, a typical range is often around 8 to 12 mEq/L without potassium or slightly higher with different methods. Because laboratory variation exists, the clinician should always rely on the local reference interval rather than a memorized value alone.
A increased anion gap points to presence of undetected anions and supports the diagnosis of acidosis. This becomes especially relevant in critical care, where elevated lactate, ketones, renal dysfunction, or toxic ingestion may call for immediate intervention.
A low anion gap is uncommon, but it can still be important. It may reflect hypoalbuminemia, laboratory variation, paraproteinemia, or uncommon measurement issues. Sometimes, a low value is a clue that the apparent acid-base balance is being distorted by changes in albumin or other serum proteins.
Bedside interpretation should answer three questions: Does the gap fall outside normal limits? Is there evidence of metabolic acidosis? And does the picture point to a single process or a mixed acid-base disorder? That framework converts a number into useful clinical interpretation.
Modifying the Anion Gap for Protein
Since albumin is a important unmeasured anion, low albumin can make the anion gap appear falsely normal or slightly elevated. For this reason albumin correction is crucial in acute care, where hypoalbuminemia is often seen due to inflammation, fluid shifts, dilution, and illness severity.
The corrected anion gap adjusts for hypoalbuminemia and helps reveal hidden acidosis. When the patient’s albumin is low, the measured gap may underestimate the true burden of unmeasured anions. In other words, a “normal” number can hide a clinically important acidotic state.
Different institutions may use alternative correction factors, but the core idea is the same: lower albumin lowers the expected anion gap. When albumin is reduced, adding a correction term can refine risk stratification and improve cause identification. This is particularly useful when evaluating sepsis, shock, malnutrition, cirrhosis, or prolonged critical illness.
When applying albumin correction, always read the result with the overall clinical picture. A corrected anion gap can reclassify a patient from normal anion gap to high anion gap metabolic acidosis, which may affect the workup and urgency of care. That is why albumin should be checked whenever the numbers and the bedside picture do not match.
High Anion Gap Metabolic Acidosis: Key Causes
A high anion gap indicates excess unmeasured acids in the blood and is a classic sign of metabolic acidosis. In critical care, the leading causes often appear quickly during bedside assessment because they are tied to shock, impaired perfusion, or acute metabolic stress.
Lactic acidosis is one of the most important causes. It may occur with sepsis, hypoperfusion, hypoxemia, seizures, or medication-related metabolic derangement. An elevated lactate should lead to rapid review of circulation, oxygen delivery, and source control when appropriate.
Ketoacidosis is another major cause, including diabetic ketoacidosis, starvation ketosis, and alcoholic ketoacidosis. These states create a high anion gap through accumulation of organic acids. In the ICU, the history, glucose pattern, and ketone measurements help clarify the picture.
Renal failure can produce high anion gap acidosis by limiting acid excretion and allowing unmeasured acids to accumulate. This can develop acutely or worsen on top of chronic kidney disease. Worsening creatinine, oliguria, and electrolyte shifts often point to the diagnosis.
Toxins must also be considered, especially in unexplained or severe cases. Toxic ingestion may involve salicylates, toxic alcohols, or other agents that create a marked metabolic acidosis. When the history is unclear, the gap can provide an early clue that life-threatening exposure is present.
In practice, a high gap should prompt rapid review of perfusion, oxygenation, renal function, glucose, ketones, and exposure history. The value itself is not the endpoint; it is a signal to identify the underlying process and respond quickly.
Standard Anion Gap Metabolic Acidosis and Differential Diagnosis Overview
A regular anion gap does not rule out acidosis. In fact, it often points toward hyperchloremic metabolic acidosis, where bicarbonate is removed or substituted by chloride, keeping the gap within the reference interval. This pattern is common in critical care and can be equally important as a high gap disorder.
Loose stools is a classic anion gap clinical significance cause because gastrointestinal bicarbonate loss causes a non-gap acidosis. Large-volume stool losses can quickly alter acid-base balance, especially when compounded by poor intake, shock, or kidney injury.
Tubular renal acidosis is another key diagnosis. It indicates impaired acid handling in the kidneys and may appear with a normal anion gap despite ongoing metabolic acidosis. The clinical context, urine studies, and serum chemistry trends help differentiate renal tubular causes from gastrointestinal bicarbonate loss.
The range of causes for normal gap acidosis also includes iatrogenic chloride load, such as large-volume saline resuscitation, and early renal dysfunction. In critical care, these patterns are often mixed, so the clinician should avoid assuming that a normal anion gap means the problem is minor or resolved.
At the bedside, the main question is whether bicarbonate has fallen because it was lost or because another ion shifted in to keep electroneutrality. That framework helps separate hyperchloremic metabolic acidosis from high gap disorders and supports next steps in treatment.
Pitfalls, Constraints, and Clinical Context
Even a properly computed anion gap can mislead if the clinical context is overlooked. A common problem is lab variation. Various analyzers and methods may yield slightly different reference interval boundaries, so the same patient can appear normal in one system and outside range in another.
Another important limitation is the combined acid-base disorder. A patient may have both elevated anion gap acidosis and metabolic alkalosis, or a elevated gap process plus corrected anion gap with albumin respiratory compensation that changes the serum bicarbonate. In these cases, the anion gap alone may fail to capture the complexity of the acid-base disorder.
The delta gap is helpful when a high anion gap is present and you want to know whether another process is also occurring. By comparing the rise in anion gap to the fall in bicarbonate, the delta gap can uncover hidden metabolic alkalosis or additional non-gap acidosis. This is especially useful in critical care, where multiple processes often overlap.
Albumin remains one of the most common sources of error. Low albumin can hide a major anion deficit, while hemoconcentration can push the result in the opposite direction. Clinical interpretation should therefore pair the electrolyte panel with albumin, renal data, perfusion markers, and bedside examination.
Finally, the anion gap is a metric for diagnostic support, not a standalone answer. It should guide cause identification, prompt serial monitoring, and improve prioritization, but it cannot replace a full acid-base assessment.
When to Repeat Labs and Increase Care
Trend monitoring is crucial when the anion gap is abnormal or the patient’s condition is shifting. A single laboratory result provides a snapshot, but serial monitoring shows whether the metabolic derangement is improving, worsening, or responding to therapy.
Order prompt repeat testing when the patient has shock, severe infection, worsening renal function, altered mental status, persistent tachypnea, or suspected toxic ingestion. In critical care, these are clues that the acid-base balance may move rapidly and that the original laboratory result may be insufficient.
An arterial blood gas is frequently helpful when the serum chemistry and the bedside picture do not align. It helps assess pH, respiratory compensation, oxygenation, and the broader acid-base disorder. Along with the electrolyte panel, it provides a more complete view of the patient’s physiology.
Increase the level of care when the gap is rising, lactate remains elevated, bicarbonate continues to fall, or the clinical status deteriorates despite treatment. A worsening gap in critical illness can indicate ongoing hypoperfusion, inadequate source control, progression of renal failure, or unresolved toxic ingestion. Timely review supports timely intervention and safer decision-making.
Common Questions About Anion Gap Calculation
Why use an anion gap calculator used for?
An anion gap calculator is designed to quickly calculate the anion gap from serum sodium, serum chloride, and serum bicarbonate. In critical care, it helps identify metabolic acidosis, suggest possible causes such as lactic acidosis or ketoacidosis, and support bedside assessment when rapid clinical interpretation is needed.
What defines the normal anion gap range?
The normal anion gap range depends on the laboratory reference interval, but many labs report a typical range around 8 to 12 mEq/L when potassium is excluded. Because laboratory variation exists, the most accurate approach is to use the reference range provided with the patient’s result.
How do you correct anion gap for albumin?
To correct the anion gap for albumin, you apply an albumin correction formula that accounts for hypoalbuminemia. Since albumin is an unmeasured anion, low albumin can make the measured gap look lower than it really is. The corrected anion gap gives a better estimate of the true acid-base burden.
What are the causes of a high anion gap in critical care patients?
Common causes of a high anion gap in critical care include lactic acidosis, ketoacidosis, renal failure, and toxins. These conditions increase unmeasured acids in the blood and often require urgent evaluation. The anion gap should be interpreted alongside the clinical picture, lactate, ketones, kidney function, and any concern for toxic ingestion.
Can a normal anion gap still indicate metabolic acidosis?
Yes. A normal anion gap can still indicate metabolic acidosis, especially hyperchloremic metabolic acidosis. This pattern may occur with diarrhea, renal tubular acidosis, or chloride-rich fluid administration. A normal gap does not rule out acid-base disorder; it only suggests that the type of acidosis may be different.